Health, Fitness,Dite plan, health tips,athletic club,crunch fitness,fitness studio,lose weight,fitness world,mens health,aerobic,personal trainer,lifetime fitness,nutrition,workout,fitness first,weight loss,how to lose weight,exercise,24 hour fitness,

Latest Post

Mechanical ventilators may cause more harm than good in a significant number of COVID-19 patients, which is a conundrum for physicians used to treating severe hypoxia — low blood oxygen — with such machines. In some cases, COVID-19 patients have oxygen levels that are so low they’re considered “incompatible with life,” yet the patients have no shortness of breath or labored breathing.1

The phenomenon has been dubbed “happy hypoxia,” a term medically known as silent hypoxemia, in which COVID-19 patients may have blood-oxygen saturation levels as low as 50% — normal blood-oxygen saturation is 95% or higher.

“There is a mismatch [between] what we see on the monitor and what the patient looks like in front of us,” Dr. Reuben Strayer, an emergency physician at Maimonides Medical Center in New York City, told Science.2

Typically, if a person has low oxygen saturation, they’ll be treated with breathing support in the form of continuous positive airway pressure, or CPAP, masks, which are often used to treat severe sleep apnea. CPAP devices regulate the pressure and level of oxygen that reaches the lungs,3 using mild air pressure to keep breathing airways open.

Bilevel positive airway pressure ventilators (BiPAP), another noninvasive device to supply pressurized air into the airways, may also be used. If oxygen saturation doesn’t increase, or in cases of acute respiratory distress syndrome (ARDS), a lung condition that’s common in severe COVID-19 cases, and which causes low blood oxygen and fluid buildup in the lungs, mechanical ventilation is often recommended.

However, research is revealing that COVID-19 patients placed on ventilators often don’t survive, leading experts to suggest the machines are being overused and patients may do better with less invasive treatments.

Over 50% of Mechanically Ventilated COVID-19 Patients Die

“Mechanical ventilation is the main supportive treatment for critically ill patients” infected with novel coronavirus 2019 (COVID-19), according to a February 2020 study published in The Lancet Respiratory Medicine.4 Yet, it’s quickly become apparent that invasively ventilated COVID-19 patients often don’t make it, and have a very high case fatality rate of more than 50%.5

The practice is widespread, nonetheless. In a case series of 1,300 critically ill patients admitted to intensive care units (ICUs) in Lombardy, Italy, 88% received invasive ventilation, but the mortality rate was still 26%.6

Further, in a JAMA study that included 5,700 patients hospitalized with COVID-19 in the New York City area between March 1, 2020, and April 4, 2020, mortality rates for those who received mechanical ventilation ranged from 76.4% to 97.2%, depending on age.7

Similarly, in a study of 24 COVID-19 patients admitted to Seattle-area ICUs, 75% received mechanical ventilation and, overall, half of the patients died between one and 18 days after being admitted.8

There are many reasons why those on ventilators have a high risk of mortality, including being more severely ill to begin with. However, given the poor outcomes, some physicians are now trying to keep patients off of ventilators as much as possible by using less-invasive alternative measures.

“Contrary to the impression that if extremely ill patients with Covid-19 are treated with ventilators they will live and if they are not, they will die, the reality is far different,” Dr. Muriel Gillick of Harvard Medical School told STAT news.9

There are risks inherent to mechanical ventilation itself, including impairment to the lung’s air sacs from high levels of oxygen and lung damage caused by the high pressure used by the machines. Long-term sedation from the intubation is another risk, one that’s difficult for some patients, especially the elderly, to bounce back from.

In cases of ARDS, the lung’s air sacs may be filled with a yellow fluid that has a “gummy” texture, making oxygen transfer from the lungs to the blood difficult, even with mechanical ventilation.

According to Gillick, “We need to ask, are we using ventilators in a way that makes sense for other diseases but not for this one? Instead of asking how do we ration a scarce resource [ventilators], we should be asking how do we best treat this disease?”10

Less Invasive Nasal Cannula May Work Better

In some cases, there’s evidence that a far less invasive nasal cannula may be sufficient to help COVID-19 patients. In a study of COVID-19 patients in China, most of the critically ill patients received high-flow nasal cannula (HFNC) oxygen therapy as a first-line treatment, and it was sufficient in the majority of cases.11

Although 41% did eventually require more intensive breathing support, noninvasive ventilation, such as BiPAP, was offered next and again succeeded in keeping most of the patients off mechanical ventilators. Ultimately, only four of the 27 patients with severe acute respiratory failure were intubated.

According to some physicians, COVID-19 patients display symptoms more in line with altitude sickness than pneumonia, such as having low levels of carbon dioxide in the blood, despite low oxygen, calling mechanical ventilation into further question.

Speaking with STAT, Dr. Scott Weingart, a critical care physician in New York and host of the “EMCrit” podcast, said, “we’ve had a number of people who improved and got off CPAP or high flow [nasal cannulas] who would have been tubed 100 out of 100 times in the past.”

But, he said, automatically putting patients on mechanical ventilators “is really bad,” adding “… I think these patients do much, much worse on the ventilator … I would do everything in my power to avoid intubating patients.”12

Are There Two Types of COVID-19 Presentations?

An April 2020 article by Drs. Luciano Gattinoni and John Marini describes two different types of COVID-19 presentations, which they refer to as Type L and Type H.13 In Type L, patients have “low lung elastance (high compliance), lower lung weight as estimated by CT scan, and low response to PEEP [positive end-expiratory pressure].” Many patients become stabilized at this stage and do not deteriorate further.

However, in some cases symptoms closer to ARDS develop. This type of presentation is defined as Type H, and includes “high elastance (low compliance), higher lung weight, and high PEEP response.”

Importantly, while one type benefits from mechanical ventilation, the other does not. Dr. Roger Seheult discusses this paper, as well as the comparison of COVID-19 to high altitude pulmonary edema, or HAPE, in the MedCram video above, once again suggesting it may turn out that mechanical ventilators are inappropriate for a majority of patients.

‘Prevent the Vent’ Approach Yields Remarkable Results

Meanwhile, doctors at University of Chicago (UChicago) Medicine reported “truly remarkable” results using high-flow nasal cannulas in lieu of ventilators.14 In fact, 24 COVID-19 patients who were in respiratory distress were given HFNCs instead of ventilators. All “fared extremely well,” and only one required intubation 10 days later.

Dr. Michael O’Connor, director of critical care medicine, called the team’s success “truly remarkable. At one point, the department had 137 COVID-19 patients, but only 27 were on ventilators. “The medical staff has avoided mechanical ventilation on 40% of patients, and extubated 50% of those who needed ventilators, O’Connor said in a news release. “It’s a phenomenal number, because in Italy, the number of extubations was much lower.”15

The team has also been combining the use of HFNCs with prone positioning, another alternative treatment that’s shown promise for treating COVID-19. Lying in the prone (face down) position, in which your chest is down and your back is up, has been shown to improve outcomes in people with severe ARDS,16 and oxygenation tends to be significantly better among patients in the prone position compared to the supine (face up) position.17

A study of critically ill COVID-19 patients in China’s Jiangsu Province recommended the use of awake prone positioning, which, the researchers noted, “showed significant effects in improving oxygenation and pulmonary heterogeneity.”18

It’s also been suggested that the physiological changes that occur with prone positioning may be even more favorable in spontaneously breathing patients than in those who are intubated.

A 2003 study found, in fact, that the prone position led to a rapid increase in partial pressure of oxygen, or PaO2, which is a measure of how well oxygen moves from the lungs to the blood, among patients with respiratory failure.19 All of the patients in the study were able to avoid mechanical ventilation.

Dr. Thomas Spiegel, medical director of UChicago Medicine’s emergency department, said, “The proning and the high-flow nasal cannulas combined have brought patient oxygen levels from around 40% to 80% and 90%, so it’s been fascinating and wonderful to see.”20

The UChicago Medicine team is using an approach they’ve dubbed “prevent the vent,” which involves using mechanical ventilation only as a last resort. “Avoiding intubation is key,” Spiegel said. “Most of our colleagues around the city are not doing this, but I sure wish other ERs would take a look at this technique closely.”21

Hyperbaric Oxygen Therapy May Prevent Mechanical Ventilation

Hyperbaric oxygen therapy (HBOT) is another treatment adjunct being explored against severe COVID-19. It works by supplying 100% oxygen in a pressurized chamber, which allows your body to absorb oxygen directly into your tissues. Since there's no airflow being forced directly into the lungs, it doesn’t cause the lung damage that mechanical ventilation can.

Dr. Kelly Thibodeaux with Opelousas General Hospital in Louisiana, which has a hyperbaric center, called HBOT “a less invasive way to deliver oxygen that doesn't require sticking a tube down the trachea.”22

Thibodeaux and colleagues explained, “Once intubated, mortality increases exponentially.”23 They’ve been deploying off-label compassionate use of HBOT as an alternative for patients that would otherwise have required ventilation, with promising results. In a case series of five patients, “dramatic improvement” was seen with HBOT. According to the article:

“All the patients recovered without the need for mechanical ventilation. Following HBOT, oxygen saturation increased, tachypnea [rapid breathing] resolved and inflammatory markers fell.

At the time of writing, three of the five patients have been discharged from the hospital and two remain in stable condition … Most importantly, HBOT potentially prevented the need for mechanical ventilation.”24

Ongoing research will be needed to determine the best course of action for individual COVID-19 cases, but it appears that starting with the least invasive options is beneficial in the majority of cases, while an increasing number of physicians are advising against mechanical ventilation whenever possible.


from Articles https://ift.tt/3esFGSe
via IFTTT
Even though the COVID-19 mortality curve has been flattened, mainstream media outlets continue to push doomsday predictions of an impending explosion of deaths. The New York Times, for example, published articles July 21,2 and July 3,3,4 2020, basically warning everyone to not get excited about plummeting mortality rates, as the trend could change at any moment.

"Why Virus Deaths Are Down but May Soon Rise," its July 2 headline states. The article goes on to claim "coronavirus trends in the United States are pretty dark right now" — based on surging case numbers, meaning positive test results, not hospitalizations or people exhibiting actual symptoms.

The article attributes the steady and relatively rapid drop-off in deaths to improved medical treatment and older people being more cautious, but warns that "Deaths may be on the verge of rising again," because "middle-aged and younger people are acting as if they're invulnerable" and have increased their social activities.

"Their increased social activity has fueled an explosion in cases over the last three weeks, which in turn could lead to a rise in deaths soon," The New York Times states,5,6 adding:

"With testing now more widespread, it's possible that the death data will lag the case data by closer to a month. (In a typical fatal case, the death comes three to five weeks after contraction of the virus.) If that's correct, coronavirus deaths may start rising again any day."

This, however, completely ignores data showing that the COVID-19 fatality rate for those under the age of 45 is “almost zero,” and between the ages of 45 and 70, it’s somewhere between 0.05% and 0.3%.7,8,9 

In other words, the fact that young and middle-aged adults are testing positive in droves is not a warning sign of an impending onslaught of deaths, as the risk of death in these age groups is minuscule. If anything, it seems to show herd immunity is building which, ultimately, will help protect the most vulnerable among us.

Why Did They Want to Flatten the Curve?

The primary justification for the tyrannical governmental interventions of COVID-19 was to slow the spread of the infection so that hospital resources would not be overwhelmed, causing people to die due to lack of medical care. These interventions were not about stopping the spread or reducing the number of people that would eventually get infected.

It was only intended to slow it down so, eventually, naturally-acquired herd immunity — the best kind — would prevent its spread. Well guess what? They have changed the narrative. That is why you now do not hear anything about flattening the curve. Instead they transitioned the fear-mongering to alarm the public that the number of “cases” are increasing.

Bear in mind that you do NOT need any test to be classified as a COVID case. All you need is a simple upper respiratory infection and you can legally be classified as a COVID-19 case to artificially inflate the totals.

Fatality Rate No Longer Cause for Hysteria

The fatality rate data given above were cited by Stanford University's disease prevention chairman Dr. John Ioannidis — an epidemiologist who has made a name for himself by exposing bad science — in a June 27, 2020, interview with Greek Reporter,10,11,12 in which he criticized global lockdown measures, saying they were implemented based on flawed modeling and grossly unreliable data.

"0.05% to 1% is a reasonable range for what the data tell us now for the infection fatality rate, with a median of about 0.25%," Ioannidis told Greek Reporter.13

"The death rate in a given country depends a lot on the age-structure, who are the people infected, and how they are managed. For people younger than 45, the infection fatality rate is almost 0%. For 45 to 70, it is probably about 0.05-0.3%.

For those above 70, it escalates substantially, to 1% or higher for those over 85. For frail, debilitated elderly people with multiple health problems who are infected in nursing homes, it can go up to 25% during major outbreaks in these facilities."

When asked whether the curve had indeed been flattened in the U.S., seeing how no health care system had been completely overwhelmed, Ioannidis answered:14

"The predictions of most mathematical models in terms of how many beds and how many ICU beds would be required were astronomically wrong. Indeed, the health system was not overrun in any location in the USA, although several hospitals were stressed. Conversely, the health care system was severely damaged in many places because of the measures taken …

Major consequences on the economy, society and mental health have already occurred. I hope they are reversible, and this depends to a large extent on whether we can avoid prolonging the draconian lockdowns and manage to deal with COVID-19 in a smart, precision-risk targeted approach, rather than blindly shutting down everything …

I hope that policymakers look at the big picture of all the potential problems and not only on the very important, but relatively thin slice of evidence that is COVID-19."

COVID-19 Close to Epidemic Threshold

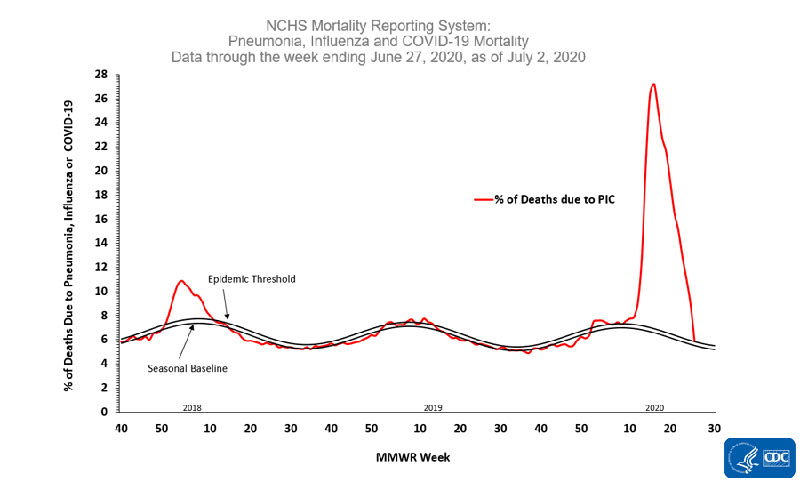
The fear-mongers also ignore recent Centers for Disease Control and Prevention statements15 saying the COVID-19 mortality — which had declined for the last 10 weeks straight — "is currently at the epidemic threshold," meaning if it slides down just a little more, COVID-19 will no longer meet the CDC's criteria for "epidemic" status.

nchs mortality reporting system

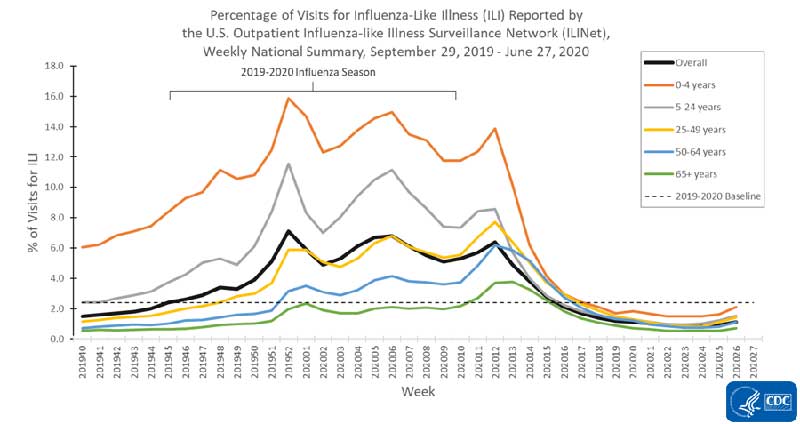
The percentage of doctors' visits for influenza-like illness (ILI) for all age groups has also dropped below the 2019-2020 baseline, as seen in the CDC graph below, published July 3, 2020.16

percentage of visits for ILI

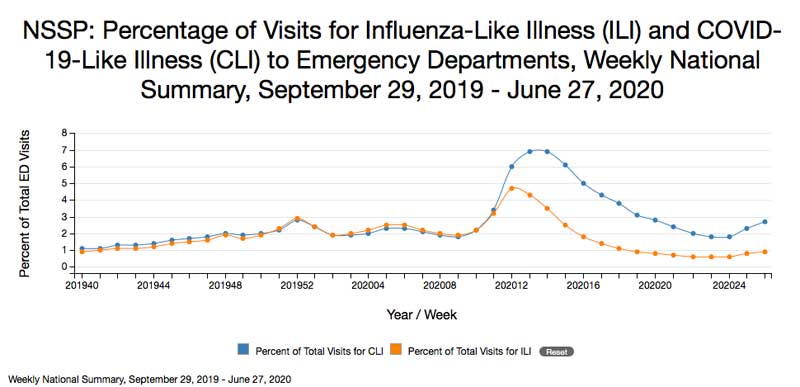
The graph below shows the percentage of visits to emergency departments, specifically, related to suspected ILI and COVID-19-like illness (CLI). While ER visits for suspected COVID-19 have seen a slight uptick, it's not an extreme increase.

nssp percentage of visits for ILI and CLI

The Truth About Increasing COVID-19 Cases

The video above reviews why the rise in COVID-19 "cases" is misleading at best, and not a viable measure of a public health threat. It presents a historical overview of what happened during the 2009 swine flu pandemic, and how it parallels the current COVID-19 pandemic.

In summary, fear of a novel illness — pandemic swine flu — led to a dramatic spike in testing, making it seem like a significant threat as many tested positive. Yet the death toll was insignificant. We're seeing the same thing happening now. Two things are driving the numbers of positive tests skyward: The sudden availability of tests, and widespread testing of asymptomatic people.

Put another way. The sharp increases in "cases" are not proof of disease spread but rather the spread of testing. When you don't have a test for the infection, you cannot tally positive cases. Hence it looked like there were virtually no COVID-19 cases in January 2020.

The sudden jump in cases in February correlates with the emergence of test kits sent out by the CDC. Once those test kits were used up, the number of "cases" again dried up. Then, once test kits became readily available again in early April, the number of cases skyrocketed — as you'd expect. But again, this doesn't mean the disease was spreading like wildfire.

It was probably in circulation throughout and countless people were already walking around with it, feeling no worse than normal. The only difference is that test kits became available and massive amounts of people — whether they had symptoms or not — were being tested.

Increased Testing = Increased 'Cases'

In short, the graphs showing "cases" in large part simply illustrate the availability of testing. Granted, even this is an oversimplification and is not going to be exact, and there's more than one reason for this. For example, during the third week of May, the CDC admitted it had combined the results from viral and antibody tests in its national results.17

This provides a really inaccurate picture, since the two tests describe very different things. The viral test is supposed to identify active infections (regardless of whether you have symptoms or not), whereas the antibody test tells you if you've been exposed to the virus in the past and fought it off by developing antibodies. Hence, an antibody test should not be counted as an active infection or active "case."

Some data18 also suggest positive test results have declined even as testing has increased. The question is, could this be an indication that people who are being tested for active infection have already fought off the virus and have antibodies? Could it be a sign of rising herd immunity?

Unfortunately, COVID-19 test data has been so mishandled and the way the data is compiled has changed enough times that it's virtually impossible to make sense of it at this point. The quality and reliability of the tests themselves, both viral and antibody, also appear to be less than stellar.

The CDC has admitted that prior exposure to coronaviruses responsible for the common cold can result in a positive COVID-19 antibody test,19 and during an April White House Coronavirus Task Force briefing, Dr. Birx explained that COVID-19 tests are "not 100% sensitive or specific," and that when prevalence is low in the community, the false positive rate will be high.

"If you have 1% of your population infected, and you have a test that's only 99% specific, that means that when you find a positive, 50% of the time will be a real positive and 50% of the time it won't be," Birx said. In other words, if the prevalence of infection in the community is 1%, about half of all positive tests will be false positives.

Only as the overall infection rate gets higher does the viral test become increasingly reliable. Who knows, perhaps this is why some of the data suggest the number of positive tests is actually decreasing even as testing continues to increase?

What Happened to the Death Toll Reporting?

As you may recall, early on, the media focused on the death toll and hospitalizations. We had daily news ticker tapes providing us with the numbers of severe and critical cases, and the number of deaths.

These statistics were used to justify draconian lockdown orders to prevent hospitals from becoming overwhelmed. Now you hear virtually nothing about hospitalizations or deaths.

It's all about the rising number of "cases," meaning infected individuals, which is to be expected when you test a population in which the virus has already infected the majority. But that doesn't mean it poses a threat, since deaths continue to drop.

It seems many are simply unwilling to accept the good news and allow the population to return to normal living. Instead, "rising cases" — especially among previous low-risk age groups — is now being used to justify continued stay-at-home orders, even though hospitals are at no risk of being overwhelmed since a vast majority of these cases are asymptomatic and need nothing in terms of health care.

In its April 13, 2020, issue, the German magazine Blauer Bote20,21 lists a collection of 75 expert opinions about the COVID-19 threat. Among them is a statement from Gerd Bosbach,22 professor emeritus of statistics, mathematics and empirical economic and social research, and author of the book, "Lying With Numbers," who said (translated from German to English using TranslationLookup.com23):24

"The tripling of the tests resulted in a little more than tripling the number of those who tested positive. This tripling was presented to the citizens as a tripling of the infected …

Far-reaching decisions require secure foundations. This is exactly what has been neglected so far. The repeated equation of the number of positively tested people with the number of infected clouded the view …

The government's standard of when measures should be weakened is based on an apparent number of infected people, which has nothing to do with reality …

So we have a muddle of terms, which is ultimately explained by the fact that we keep talking about infected people instead of positive people. The high numbers remain in memory, such as the mortality rate of 3.4% stated by the WHO. And that creates fear …

We should ensure that the media do not use the power of images to generate emotions that influence our judgment. If you get pictures of coffins and death departments from Italy or pictures of completely empty shelves, then their effects exceed the facts mentioned."

Herd Immunity Likely Much Higher Than Suspected

In related news, several recent studies suggest a majority of the population may already have immunity against COVID-19, via one mechanism or another. According to a Swiss study,25,26 SARS-CoV-2-specific antibodies are only found in the most severe cases — about 1 in 5. That suggests COVID-19 may in fact be five times more prevalent than suspected. This also means it may be five times less deadly than predicted. According to the authors:

"When symptomatic, COVID-19 can range from a mild flu-like illness in about 81% to a severe and critical disease in about 14% and 5% of affected patients, respectively."

They also found that even though people who had been exposed to COVID-19 had SARS-CoV-2-specific immunoglobulin A (IgA) antibodies in their mucosa, there were no virus-specific antibodies in their blood.

IgA is an antibody that plays a crucial role in the immune function of your mucous membranes, while IgG is the most common antibody that protects against bacterial and viral infections and is found in blood and other bodily fluids. As explained by the authors:27

"As with other coronaviruses, symptomatic SARS-CoV-2 disease causes an acute infection with activation of the innate and adaptive immune systems. The former leads to the release of several pro-inflammatory cytokines, including interleukin-6 …

Subsequently, B and T cells become activated, resulting in the production of SARS-CoV-2-specific antibodies, comprising immunoglobulin M (IgM), immunoglobulin A (IgA), and immunoglobulin G (IgG).

Whereas coronavirus-specific IgM production is transient and leads to isotype switch to IgA and IgG, these latter antibody subtypes can persist for extended periods in the serum and in nasal fluids. Whether SARS-CoV-2-specific IgG antibodies correlate with virus control is a matter of intense discussions."

Majority of People Appear Resistant to COVID-19

Another study28,29 published in the journal Cell found 70% of samples from patients who had recovered from mild cases of COVID-19 had resistance to SARS-CoV-2 on the T-cell level. Curiously, 40% to 60% of people who had not been exposed to SARS-CoV-2 also had resistance to the virus on the T-cell level.

According to the authors, this suggests there's "cross-reactive T cell recognition between circulating 'common cold' coronaviruses and SARS-CoV-2." In other words, if you've recovered from a common cold caused by a particular coronavirus, your humoral immune system may activate when you encounter SARS-CoV-2, thus rendering you resistant to COVID-19.

May 14, 2020, Science magazine reported30 these Cell findings, drawing parallels to another earlier paper31 by German investigators that had come to a similar conclusion. That German paper,32 the preprint of which was posted April 22, 2020, on Medrxiv, found helper T cells that targeted the SARS-CoV-2 spike protein in 15 of 18 patients hospitalized with COVID-19.

Yet another study,33,34,35 this one by researchers in Singapore, found common colds caused by the betacoronaviruses OC43 and HKU1 might make you more resistant to SARS-CoV-2 infection, and that the resulting immunity might last as long as 17 years.

The authors suggest that if you've beat a common cold caused by a OC43 or HKU1 betacoronavirus in the past, you may have a 50/50 chance of having defensive T-cells that can recognize and help defend against SARS-CoV-2.

81% of Unexposed Individuals May Be Resistant to SARS-CoV-2

Two additional studies suggesting herd immunity is near were reported36 by Reason, July 1, 2020. These include a Swedish study,37,38 which found "SARS-CoV-2 elicits robust memory T cell responses akin to those observed in the context of successful vaccines, suggesting that natural exposure or infection may prevent recurrent episodes of severe COVID-19 also in seronegative individual." Similarly, a German study39 concluded:

"SARS-CoV-2-specific T-cell epitopes enabled detection of post-infectious T-cell immunity, even in seronegative convalescents. Cross-reactive SARS-CoV-2 T-cell epitopes revealed preexisting T-cell responses in 81% of unexposed individuals, and validation of similarity to common cold human coronaviruses provided a functional basis for postulated heterologous immunity in SARS-CoV-2 infection."

Flattening the Curve Was a Fool's Errand

So far, many efforts to curb COVID-19 infection have proven to be ill advised. Evidence shows the illness spreads mostly indoors,40,41,42 for example, casting doubt on the sanity of closing parks and beaches, especially during the summer. As reported by The Baltimore Sun,43 scientists are now considering using ultraviolet light to eradicate SARS-CoV-2 in indoor air. Step outside, and you get that effect for free.

The total all-cause mortality is not significantly different than in previous years as discussed by my interview with Denis Rancourt. Many other deaths have been shifted to COVID-19, bringing a high spike in deaths, but when you look at the area under the curve for total deaths, it really doesn't differ from previous years.

This was also echoed by the American Institute for Economic Research.44 Back in April 2020 they referred to the COVID-19 pandemic as "An egregious statistical horror story" that resulted in "a vandalistic lockdown on the economy," which:

"… would have been an outrage even if the assumptions were not wildly astronomically wrong. Flattening the curve was always a fool's errand that widened the damage …

The latest figures on overall death rates from all causes show no increase at all. Deaths are lower than in 2019, 2018, 2017 and 2015, slightly higher than in 2016. Any upward bias is imparted by population growth.

Now writing a book on the crisis with bestselling author Jay Richards, [statistician William] Briggs concludes: 'Since pneumonia deaths are up, yet all deaths are down, it must mean people are being recorded as dying from other things at smaller rates than usual.' Deaths from other causes are simply being ascribed to the coronavirus.

As usual every year, deaths began trending downward in January. It's an annual pattern. Look it up. Since the lockdown began in mid-March, the politicians cannot claim that their policies had anything to do with the declining death rate.

A global study45 published in Israel by Professor Isaac Ben-Israel, chairman of the Israeli Space Agency and Council on Research and Development, shows that 'the spread of the coronavirus declines to almost zero after 70 days — no matter where it strikes, and no matter what measures governments impose to try to thwart it.'

In fact, by impeding herd immunity, particularly among students and other non-susceptible young people, the lockdown in the U.S. has prolonged and exacerbated the medical problem. As Briggs concludes, 'People need to get out into virus-killing sunshine and germicidal air.'"


from Articles https://ift.tt/2WhXaKD
via IFTTT

The cold weather is well and truly here, so you’re likely to see a lot of “immune-boosting”  juices, recipes and supplements kicking around the internet. But dietitian Melissa Meier wants you to know why that terminology is just plain wrong. She shares 10 foods to consume if you want a “strong” immune system, instead. 

from Nutrition | body+soul https://ift.tt/304su0M

MKRdezign

Contact Form

Name

Email *

Message *

Powered by Blogger.
Javascript DisablePlease Enable Javascript To See All Widget