Health, Fitness,Dite plan, health tips,athletic club,crunch fitness,fitness studio,lose weight,fitness world,mens health,aerobic,personal trainer,lifetime fitness,nutrition,workout,fitness first,weight loss,how to lose weight,exercise,24 hour fitness,
Labels
Technology
New Post
[recent][newsticker]
Latest Post
Top Health News -- ScienceDaily
Aging
Alzheimer's
Articles
Articles : Asthma
Articles : CAFO
Articles : Children's Health
Articles : Cholesterol
Articles : Emotional Health
Articles : Fibromyalgia
Articles : GMO
Articles : Heart Health
Articles : Hormones
Articles : Internal Videos
Articles : Interviews
Articles : Men's Health
Articles : Politics
Articles : Thyroid Disease
Articles : Vaccines
Autism
best natural health source
Children's Health
Detoxification
Diabetes
Diet | body+soul
Diet and Weight Loss News -- ScienceDaily
Digestive Diseases
Dite
Dite & weight loss
Drug Industry
Drugs
EFT
EMF
Emotional Health
Finances
fitness
Fitness | body+soul
Fitness/Exercise
Fluoride
Food
Fructose/Sugar
Gardening
Harvard Health Blog
Health
Health | body+soul
Health and Wellness
health news
health tips
Heart Health
information
Joint Support
Juicing
Men's Health
news
Nutrition
Nutrition | body+soul
Pollution
Raw Milk
Soy
Supplements
Swine Flu
Technology
Thyroid Disease
Top Health
Top Health News -- ScienceDaily
Under Armour
Vaccines
Weight Management
women's health
Women's Health News -- ScienceDaily
work place health
Workplace Health News -- ScienceDaily
CNN Spreads Deadly Lies About Vitamin D for COVID-19
May 31, 2020, I posted an interview with three vitamin D experts in which we discuss the importance of vitamin D for preventing COVID-19 infection. A few days earlier, May 27, CNN published a report1 that could have deadly consequences if believed, claiming taking vitamin D supplements “can hurt a lot.”
The article was written by Sandee LaMotte — a medical producer and writer for CNN and executive producer of video at pharma-biased WebMD. Three other CNN reporters, Emma Reynolds, Shelby Lin Erdman and Rob Picheta, also contributed to the story.
The article quotes Robin May, director of the British Institute of Microbiology and Infection as saying:2 "To date, there is no evidence that very high vitamin D levels are protective against COVID-19 and consequently medical guidance is that people should not be supplementing their vitamin D levels beyond those which are currently recommended by published medical advice."
CNN Cites Vitamin D Recommendations Known To Be Incorrect
LaMotte cites dosing recommendations from the Institute of Medicine’s National Academies' Food and Nutrition Board — a nongovernmental organization — which advises a daily dose of just 600 IUs for anyone over the age of 4, and 800 IUs for those over 70. In the U.K., the daily dose is a meager 400 IUs a day.
Nowhere does the article mention that the IOM’s dosage recommendations are based on the levels thought to be adequate only for bone health.3 They do not take into account the amount of vitamin D you need to prevent influenza, heart- or liver- disease, respiratory infections, cancer, or any of the many other diseases that have a clearly documented link to vitamin D deficiency.
LaMotte also fails to mention that the IOMs recommendations are off by a factor of 10 due to a mathematical error, as reported by Science Daily4 in 2015. Two papers5,6 confronting this issue have been published in the journal Nutrients, both of which call for the IOM to correct its mistake, lest public health suffer.
So, if IOM were to simply go back and correct this egregious mistake, the “conventional medical advice” would be to take 6,000 IUs a day, or 8,000 IUs if you’re over 70. These dosages are quite close to the so-called “high-dose” recommendations suggested by many vitamin D researchers.
The statement that there is “no evidence that very high vitamin D levels are protective against COVID-19” is equally misleading, considering a number of reports from COVID-19 researchers now show that vitamin D appears to play a significant role in this infectious disease.
Similarly, researchers demonstrated that the age-specific case fatality rate of COVID-19 was highest in Italy, Spain and France — European countries with the highest incidence of severe vitamin D deficiency.7
In the video below, published May 11, 2020, on Medscape.com, Dr. JoAnn E. Manson, professor of medicine and chief of division of preventive medicine at Harvard Medical School, discusses the protective role of vitamin D against COVID-19.
Vitamin D Deficiency Increases Risk of Positive COVID-19 Test
A May 2020 paper8 published on the preprint server MedRxiv (which means it’s still awaiting peer-review) presents evidence that vitamin D deficiency increases the risk of testing positive for COVID-19 infection. As reported by News Medical Life Sciences:9
“The study by researchers at the University of Chicago looked at over 4,300 patients with COVID-19 of whom 499 had been tested for vitamin D levels in the previous year. Based on this, they were divided into likely deficient (25%), likely adequate (58%), and uncertain (16%).
Vitamin D deficiency was diagnosed by ‘the most recent 25-hydroxycholecalciferol <20ng/ml or 1,25-dihydroxycholecalciferol <18pg/ml within one year before COVID-19 testing.’
Multiple variables were analyzed in this study. The researchers found that people with vitamin D deficiency at the last testing, and who did not receive higher doses of vitamin D (keeping them deficient in all probability), are much more likely to be infected with the virus than those with probably sufficient levels. The corresponding rates of infection were 22% vs. 12%.”
Similarly, a May 6, 2020, report10 in the journal Nutrients pointed out that vitamin D concentrations are lower in patients with positive PCR (polymerase chain reaction) tests for SARS-CoV-2. As noted in this report, which retrospectively investigated the vitamin D levels obtained from a cohort of patients in Switzerland:11
“In this cohort, significantly lower 25(OH)D levels were found in PCR-positive for SARS-CoV-2 (median value 11.1 ng/mL) patients compared with negative patients (24.6 ng/mL); this was also confirmed by stratifying patients according to age >70 years. On the basis of this preliminary observation, vitamin D supplementation might be a useful measure to reduce the risk of infection.”
Low Vitamin D Boosts Risk of Serious COVID-19 Infection
According to an editorial review12,13 by Irish researchers, people with vitamin D deficiency appear to be far more prone to severe COVID-19 infections. According to the authors:14
“When mortality per million is plotted against latitude, it can be seen that all countries that lie below 35 degrees North have relatively low mortality. Thirty‐five degrees North also happens to be the latitude above which people do not receive sufficient sunlight to retain adequate vitamin D levels during winter. This suggests a possible role for vitamin D in determining outcomes from COVID‐19 …
There are considerable experimental data showing that vitamin D is important in regulating and suppressing the inflammatory cytokine response of respiratory epithelial cells and macrophages to various pathogens including respiratory viruses …
It is important to note that the hypothesis is not that vitamin D would protect against SARS‐CoV‐2 infection but that it could be very important in preventing the cytokine storm and subsequent acute respiratory distress syndrome that is commonly the cause of mortality …
The evidence supporting a protective effect of vitamin D against severe COVID‐19 disease is very suggestive, a substantial proportion of the population in the Northern Hemisphere will currently be vitamin D deficient, and supplements, for example, 1,000 international units (25 micrograms) per day are very safe.
It is time for governments to strengthen recommendations for vitamin D intake and supplementation, particularly when under lock‐down.”
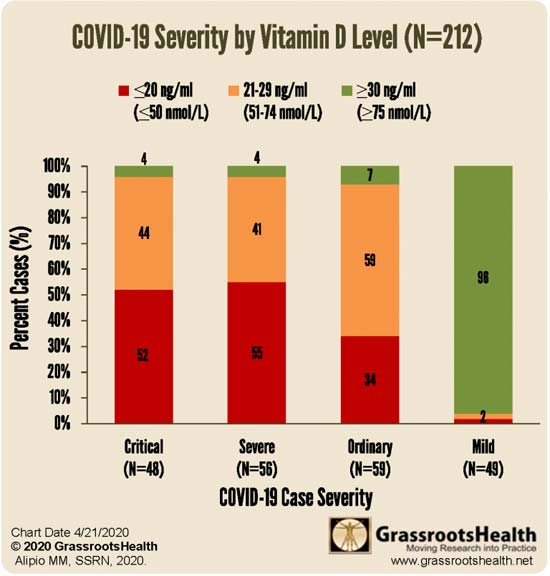
Similarly, Mark Alipio with GrassrootsHealth conducted a retrospective multicenter study15,16 involving 212 patients in Southeast Asia who had COVID-19. He too found a strong correlation between vitamin D levels and disease severity. Those with the mildest disease had the highest vitamin D levels, and vice versa.
Normal vitamin D levels were defined as greater than 30 ng/ml; insufficient levels were defined as 21 to 29 ng/ml; anything below 20 ng/mL was considered deficient. While Grassroots Health research has determined that 40 ng/mL is the lower edge of optimal, with 60 ng/mL to 80 ng/mL being ideal for health and disease prevention, the benefit of having a vitamin D level above 30 ng/mL was clear.
Low Vitamin D Levels Linked to Increased COVID-19 Mortality
The epidemiology of COVID-19 provides evidence that vitamin D might be helpful in reducing risk associated with COVID-19 deaths.17 A May 6, 2020, report18 published in Aging Clinical and Experimental Research (its prepublication featured in the Daily Mail May 119) found that countries with lower vitamin D levels also have higher mortality rates from COVID-19. According to the authors:20
“The Seneca study showed a mean serum vitamin D level of 26 nmol/L in Spain, 28 nmol/L in Italy and 45 nmol/L in the Nordic countries, in older people. In Switzerland, mean vitamin D level is 23 nmol/L in nursing homes and in Italy 76% of women over 70 years of age have been found to have circulating levels below 30 nmol/L.
These are the countries with high number of cases of COVID-19 and the aging people is the group with the highest risk for morbidity and mortality with SARS-CoV2.”
In the preprint version21 of this paper, the authors concluded: “We believe that we can advise vitamin D supplementation to protect against SARS-CoV2 infection.” In the final version,22 they toned down the recommendation to: “We hypothesize that vitamin D may play a protective role for COVID-19.”
Another study,23,24 which looked at data from 780 hospital patients in Indonesia, found those with a vitamin D level between 20 ng/mL and 30 ng/mL had a sevenfold higher risk of death than those with a level above 30 ng/mL, and having a level below 20 ng/mL was associated with a 12 times higher risk of death.
Vitamin D Is a Simple Strategy That Can Save Lives
In a May 18, 2020, letter25 to the Federal Chancellor of Germany, Angela Merkel, retired biochemist Bernd Glauner and Lorenz Borsche highlight these and other studies26 and ask whether a nationwide supply of vitamin D has been considered in Germany.
“Until a vaccine is available, vitamin D supplementation could be a preventive measure that should be discussed to reduce the lethality of covid-19. The available studies also suggest that vitamin D shock treatment may protect patients already infected and hospitalized with Covid-19 from lethal sepsis,” they write.
The following graph is included in the letter.
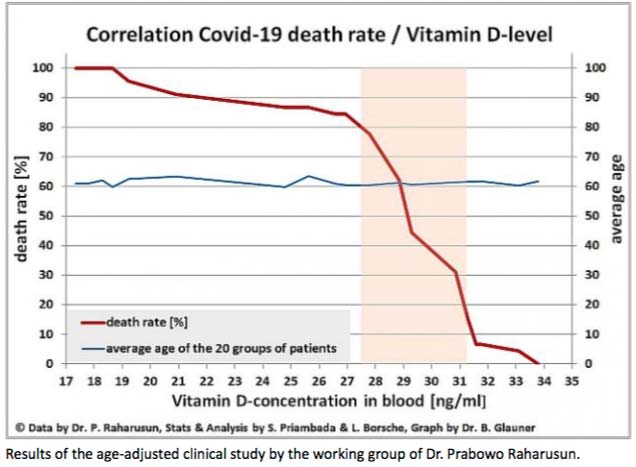
Glauner and Borsche continue:27
“… Scientific and clinical studies suggesting an alternative treatment option are apparently ignored. One of these promising approaches is the treatment with vitamin D. The available studies on Covid-19 patients suggest that a large proportion of deaths could possibly be prevented and severe courses could be reduced to milder ones …
This way would be easy and does not cause high costs. It would be sufficient to measure the vitamin D level in Covid-19 infected persons, hospital staff and risk patients and, if necessary, to raise it to healthy levels well above 35 ng/ml. In any case, no comparison to the enormous costs of the lockdown. This could possibly save us another lockdown and many more Covid-19 fatalities.”
No, Vitamin D Supplementation Is Not Dangerous
The CNN article is just another propaganda COVID-19 narrative of mainstream media. This egregious behavior is similar to the hydroxychloroquine paper published in The Lancet that the WHO has used to discredit and stop using hydroxychloroquine for COVID-19. Over 100 scientists question the ethics and standards of this incredibly shoddy study.28
Probably the most serious mistake in LaMotte’s CNN article are her claims that vitamin D supplementation “can hurt a lot.” She claims “too much vitamin D can lead to a toxic buildup of calcium in your blood, causing confusion, disorientation and problems with heart rhythm, as well as bone pain, kidney damage and painful kidney stones.”
She makes those claims without a) citing or referencing any supporting evidence, b) clarifying that the “toxic buildup of calcium” (hypercalcemia) is caused by insufficient vitamin K2 in relation to vitamin D, not vitamin D per se (a fact that is now well-established) and c) without specifying what “too much” actually might be.
A review29 of published trials have demonstrated there are no toxicity symptoms — including hypercalcemia — at dosages up to 10,000 IU of vitamin D3 per day, even when used long-term. A more recent paper found that Intakes of vitamin D up to 15,000 IU/day are safe.30
In my search for horror stories, I discovered a case paper31 published in 2011, which presented the cases of 10 adult patients diagnosed with hypercalcemia in relation to vitamin D supplementation.
Symptoms listed in this paper include vomiting, polyuria (excessive urination), polydipsia (excessive thirst), hypercalcemia (excessive calcium levels), encephalopathy (brain damage or disease causing memory loss, personality changes or seizures, for example) and kidney dysfunction.
It sounds scary, but when you consider that these patients were taking MILLIONS of units of vitamin D — specifically, 3,600,000 (3.6 million) IUs and 210,000,000 (210 million) IUs over the course of one to four months (median two months) — you start to see just how wrong it is to warn people off vitamin D supplements.
For example, the dosages these people were getting would be like taking 30,000 IUs of vitamin D per day for 120 days on the lowest end, or 7 million IUs a day for 30 days on the extreme upper end. No one is recommending you take these kinds of dosages, especially not for extended periods of time.
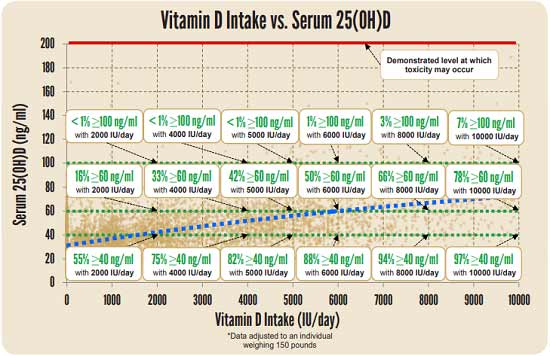
Many may need 10,000 IUs a day — which is safe — to get their level above 60 ng/mL. The maintenance dose, however, is typically lower. To determine your ideal dose, you need to get your blood tested, ideally twice a year. The level you’re looking for is between 60 ng/mL and 80 ng/mL. As of right now, there does not appear to be any significant benefit to levels higher than 80 ng/mL.
REALLY IMPORTANT: Optimize Your Vitamin D Level Before Fall!
Experts are already warning that SARS-CoV-2 may reemerge in the fall when temperatures and humidity levels drop, thereby increasing the virus’ transmissibility.
I am in the process of writing an even more comprehensive and detailed report on vitamin D in the prevention of COVID-19 and I hope to enlist ALL of you to participate as an army to go out and tell all your friends and family and get them on board to get their vitamin levels optimized.
Once you have done that, the next step is to encourage pastors of black churches to get their congregations on board. It will also be important to reach out to mangers of nursing homes and assisted living facilities as both of these populations have notoriously low vitamin D levels that put them at greater risk of COVID-19.
You now have a known “deadline” for optimizing your vitamin D level. Historically, December typically has highest flu activity in the U.S.,32 but it would probably be good to aim for October, or maybe even earlier depending on your location.
To improve your immune function and lower your risk of viral infections, you’ll want to raise your vitamin D to a level between 60 nanograms per milliliter (ng/mL) and 80 ng/mL by fall. In Europe, the measurements you’re looking for are 150 nanomoles per liter (nmol/L) and 200 nmol/L.
Again, optimizing your vitamin D is particularly important if you have darker skin, as darker skin places you at higher risk for vitamin D deficiency — and serious COVID-19 infection. What’s more, the elderly tend to lose the ability to synthesize vitamin D from sun exposure, and therefore tend to have suboptimal levels even if they spend plenty of time outdoors.
One of the easiest and most cost-effective ways of measuring your vitamin D level is to participate in the GrassrootsHealth’s personalized nutrition project, which includes a vitamin D testing kit, either alone or in combination with the omega-3 test. This is done in the convenience of your home.
You’ll learn your nutrient levels, how effective your health actions are, and you’ll be able to see thousands of other data sets that allow you to compare health outcomes important to you. Knowledge is empowerment, and that is particularly true during this pandemic. To make sure your immune system has a chance to work optimally, follow these three steps.
Step 1: Measure Your Vitamin D
First, find out what your base level is. This is done with a simple blood test. An easy and cost-effective way of doing this is to order GrassrootsHealth’s vitamin D testing kit.
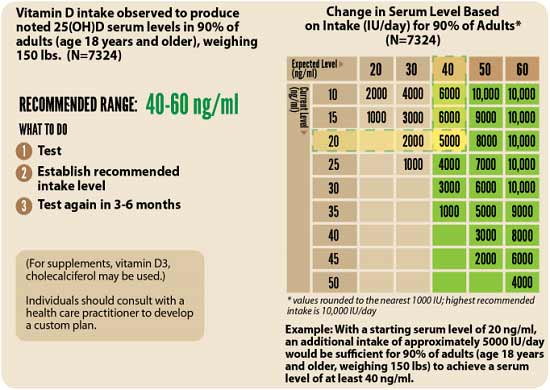
Once you know what your blood level is, you can assess the dose needed to maintain or improve your level. Again, the ideal level you’re looking for is above 40 ng/mL, and ideally between 60 ng/mL and 80 ng/mL (European measurement: 100 nmol/L or, ideally, 150 nmol/L to 200 nmol/L).
The easiest way to raise your level is by getting regular, safe sun exposure, but if you’re very dark-skinned, you may need to spend about 1.5 hours a day in the sun to have any noticeable effect.
Those with very light skin may only need 15 minutes a day, which is far easier to achieve. Still, they too will typically struggle to maintain ideal levels during the winter. So, depending on your situation, you may need to use an oral vitamin D3 supplement. The next question then becomes, how much do you need?
Step 2: Assess Your Individualized Vitamin D3 Dosage
The following chart can provide you with a basic starting point:
You can fine-tune your dosage further by taking into account your baseline vitamin D level. To do that, you can either use the chart below, or use GrassrootsHealth’s Vitamin D*calculator. To convert ng/mL into the European measurement (nmol/L), simply multiply the ng/mL measurement by 2.5.
How to Calculate Your Vitamin D From Sun Exposure
To calculate how much vitamin D you may be getting from regular sun exposure in addition to your supplemental intake, consider using the DMinder app,33 created by Dr. Michael Holick, author of “The Vitamin D Solution: A Three-Step Strategy to Cure Our Most Common Health Problems.” The free app is available for iPhone and android in the Apple store and Google play respectively. As explained by imedicalapps.com:34
“The app attempts to calculate a patients’ vitamin D level based on demographics imputed when first opening the app and then updates the level based on either actual lab draws or data from the app. The app even uses the phone’s GPS and clock to determine the ‘best’ time of day for a patient to get the required sun exposure for vitamin D skin conversion.”
Step 3: Retest
Lastly, you’ll need to remeasure your vitamin D level in three to six months, to evaluate how your sun exposure and/or supplement dose is working for you. Not only will optimizing your vitamin D be an important strategy for you and your family, but it would be really helpful to start thinking about your community as well.
If you can, speak to pastors in churches with large congregations of people of color and help them start a program getting people on vitamin D. Doing so could save far more lives than any vaccine program.
If you have a family member or know anyone who is in an assisted living facility you could meet with the director of the program and encourage them to get everyone tested or at least start them on vitamin D.

from Articles https://ift.tt/2Yb7swq
via IFTTT
Weekly Health Quiz: Magnesium, Spotify and YouTube
1 H.R. 6666, the COVID-19 Testing, Reaching And Contacting Everyone (TRACE) Act may end up violating which of the following constitutional rights?
- Fourth and Fifth amendments
- Eighth Amendment
- Ninth Amendment
- All of the above
H.R. 6666 does not ensure privacy. It also sets the stage for multiple violations of our constitutional rights, including the Fourth, Fifth, Eighth and Ninth amendments. Learn more.
2 What distinguishes SARS-CoV-2 from all other known coronaviruses?
- The presence of a furin cleavage site on its spike protein
CoV-2 is the only coronavirus with a furin cleavage site. Not even distant relatives of CoV-2 have it, and the coronaviruses that do have it share only 40% of CoV-2's genome. Some experts have pointed out that this novel function couldn't possibly have arisen naturally. Learn more.
- The absence of a furin cleavage site on its spike protein
- The presence of an S1 section on its spike protein
- The absence of an S2 section on its spike protein
3 Which of the following are symptoms of magnesium deficiency?
- Backache
- Depression/anxiety
Symptoms of magnesium deficiency can include many mental issues such as depression, confusion and agitation. Learn more.
- Poor hair/nail growth
- Stunted growth in children
4 Who recently signed an exclusivity contract with Spotify "in protest" against YouTube censorship?
- Alex Jones
- Brene Brown
- Joe Rogan
Joe Rogan has signed a $100 million exclusivity contract with Spotify for his Joe Rogan Experience Podcast. According to Rogan, the move is his way to strike back against YouTube censorship. Learn more.
- Katie Couric
5 This type of oral vitamin C may enhance bioavailability of vitamin C, raising peak plasma concentration by 70% compared to other forms:
- High-dose
- Gel caps
- Vitamin C with bioflavonoids
- Liposomal
"The average peak plasma concentration of vitamin C in the participants who took the free form was approximately 180 micromoles per liter of blood. However, among those who took the liposomal form, the average peak plasma concentration was 300 micromoles per liter of blood, a 70% difference," she says. Learn more.
6 Which of the following is one of the oldest organizations providing objective, unbiased information about vaccines to help people make informed medical choices?
- The National Vaccine Information Center (NVIC)
The National Vaccine Information Center (NVIC) is the oldest and largest consumer-led nonprofit organization in the U.S. providing accurate and objective information to prevent vaccine injuries and deaths through public education and help people make informed health choices. Learn more.
- The National Institutes of Health (NIH)
- Gavi, The Vaccine Alliance
- The World Health Organization (WHO)

from Articles https://ift.tt/2MGr7yZ
via IFTTT
Data Show Cannabis Terpenes May Slow COVID-19 Infection
The body of scientific evidence demonstrating the medicinal value of cannabis continues to grow and become more compelling. Your body makes its own cannabinoids that interact with the receptors in your brain, lungs, liver, kidneys, immune system and other organs, tissues and blood vessels. They are activated by the therapeutic and psychoactive properties of the plant.1
Cannabis can be bred to have high levels of cannabidiol (CBD) and low levels of tetrahydrocannabinol (THC) content. THC has the psychoactive activity, while CBD has no psychoactive properties. The plant also contains terpenes, which are the oils that give cannabis its distinctive flavor and odor.
To date, hundreds of compounds have been identified in the plant,2 including cannabinoids, terpenes and other phytochemicals. In China, Cannabis sativa has a long history of recorded use, dating back nearly 2,000 years.3 In old texts, researchers have found references to application of cannabis for pain and mental illness.
Much of the current research has been on the relationship of CBD and THC to inflammation. However, during the first severe acute respiratory syndrome (SARS) epidemic in 2003 to 2004, researchers investigated the effects of terpenes found in cannabis and other plants and found they have antiviral properties.4
Twofold Testing on Specific Strains of Cannabis Sativa
Angiotensin converting enzyme 2, or ACE2 receptors, provide an entry point for SARS-CoV-2 to infect the human cell.5 This receptor is found on the surface of many types of cells, but most specifically in the oral and nasal mucosa, lungs, intestinal tract, liver, kidney and brain.6
The virus uses spike-like proteins to bind with the ACE2 receptor, giving it entrance into the cell. Scientists are researching ways to use this pathway to modulate the entry of the virus into the cell with the hope of decreasing an individual's susceptibility to the disease. One team investigated the effect that cannabis has on ACE2 receptors.7
The researchers used extracts from hundreds of lines of Cannabis sativa in a computer-generated model of human mouth, airway and intestinal tissue. Their preliminary data show that the extract of 13 lines of Cannabis sativa that were high in CBD could keep the virus out of the cells.
They acknowledge that further large-scale validation is necessary, but the initial result may provide useful preliminary evidence that adding these extracts could be used as adjunct therapy.
They suggest developing preventive treatments, such as the use of mouthwash, that may reduce viral entry through the oral mucosa. One of the researchers, Dr. Igor Kovalchuk, spoke with a reporter form the Calgary Herald about the results:8
"A number of them have reduced the number of these (virus) receptors by 73 per cent, the chance of it getting in is much lower. If they can reduce the number of receptors, there's much less chance of getting infected. It will take a long time to find what the active ingredient is — there may be many."
Past Data Support Antiviral Activity of Some Terpenes
A second team from the Israel Institute of Technology led by Dedi Meiri, Ph.D., spoke with a reporter from Health Europa about a formulation of terpenes extracted from cannabis being tested against Stars CoV-2.9
Health Europa reported after the SARS outbreak in 2002 that researchers found terpenes were effective antiviral agents and could reduce the severity and impact of an infection by preventing the virus from penetrating human cells. Meiri said his lab is approved to conduct an investigation and colleagues are currently underway promoting two lines of study based on cannabis. He explained the initial study:
"First, we will try to identify the plant's own molecules that are capable of suppressing the immune response to the COVID-19 coronavirus — which causes inflammation and severe disease — to lower the immune system response without suppressing it, thereby providing better complementary treatment to the steroids, which completely suppress the immune system."
In the second study, researchers will be looking at how the cannabis molecule may affect the viral process of infecting cells through the ACE2 receptor. Researchers have been looking for a way to impact ACE2 receptors since the first SARS outbreak in 2003.10
The team hopes terpenes found in cannabis will help modulate the cytokine storm — overreaction of the immune system — associated with COVID-19, known to cause organ system failure leading to death.11
In 2007, a study was published in the Journal of Medicinal Chemistry in which researchers evaluated 221 phytocompounds for their activity against SARS. They induced cytopathogenic effects on cell cultures and tested terpenoids, lignoids and curcumin against the cell cultures.12
The data showed that 22 compounds could inhibit 50% of the pathogenic cell proliferation and viral replication. The researchers suggest specific types of diterpenoids and lignoids have a powerful effect against the SARS virus in vitro.
Scientists have also found terpenoids may have a synergistic effect in cannabis that may help to treat pain, inflammation and bacterial infections in combination with other phytochemicals.13
Social Media Headlines Overstated Current Facts
While the research is promising, some who republished certain information overstated the facts. The headline "Cannabis May Stop Coronavirus From Infecting People, Study Finds" first appeared on the website MerryJane.14 The headline was quickly picked up and passed through social media, until Facebook flagged it for "false news and misinformation" as reported by Politifact.15
However, while the headline may have been misleading, the content in the MerryJane article followed the research, communicating the data and the shortcomings of the study. Forbes Magazine also picked up the story. In their article the writer linked an article in the New York Post16 with the viral content on Facebook and finally to a quote that appears to have come from the New York Post:17
"And a rally 'vaguely' timed, as MarketWatch reporter Max Cherney observed, with the New York Post's publication Thursday of its take on the big story that had gone viral on Facebook earlier that month, and was later flagged as fake news: the claim, first made in a preclinical paper published in April, by Canadian scientists that certain high CBD strains of 'cannabis could prevent and treat coronavirus.'"
Kovalchuk spoke with a reporter from Politifact and confirmed the headline was an overstatement.18 Kovalchuk was also interviewed by the Forbes reporter and said:19
"It reduces the possibility to get infected. I never said it would prevent or block it entirely. It is a possible treatment. A treatment is not a cure. When [news reports] say it treats COVID, or can potentially treat COVID, they are absolutely right."
Terpene-Extract May Boost Hand Cleaning for COVID-19
In mid-April, Vanguard Scientific announced they had developed a new hand cleaner made from terpene extract. The hand cleaner uses an alcohol-based sanitizer following CDC recommendations, into which the company added terpenes derived from cannabis. They believe this "may boost the mixture's antibacterial, antimicrobial and antiviral effects."20
The company also began an open source project in which they released the recipe and the standard operating procedures for free. They've called it Project Terpenes-Clean and hope it will bring together scientists from around the world to develop a powerful hand cleaner. Matthew Anderson is CEO of Vanguard Scientific and commented on the program and the product:21
"Like all industries, the botanical extraction industries have been hit hard by the COVID-19 crisis. As a company working with clients to target specialized botanical extracts, we've focused on finding opportunities to help in the fight against the virus.
We know that traditional healers have used plant-derived compounds as powerful medicine for centuries, so we're offering our expertise to the rest of the industry so others can join us in creating a soap-less hand cleaner that leverages industry science and increases the supply of hand cleaning products.
Open source drives innovation while promoting collaboration and adoption to ensure maximum transparency: anyone can inspect an open source project for errors or inconsistencies and that matters in regulated industries."
Cannabinoids Affect Cardiovascular System
Researchers presented data at a 2019 meeting of the American Heart Association showing that young people who had been diagnosed with a cannabis use disorder had a 47% to 52% higher risk of being hospitalized for an irregular heartbeat, also known as an arrhythmia, as compared to those without the disorder.22
In the study, researchers use data from more than 67 million hospital patients. The effect appeared to be dependent on the dose. Lower doses were linked to a rapid heart rate while higher doses were linked to heart rates that were too slow.23
Results from a second study showed that those who used cannabis for more than 10 days a month had a 2.5 times increased risk of stroke compared to nonusers.24 Those who also smoked cigarettes or e-cigarettes had an even higher risk — more than three times that of nonusers.
Your body has cannabinoid receptors in the brain, lungs, liver, kidneys and other organs and tissues, as well as blood vessels. Harvard Medical School describes the action cannabinoids have on heart health:25
"One of the few things scientists know for sure about marijuana and cardiovascular health is that people with established heart disease who are under stress develop chest pain more quickly if they have been smoking marijuana than they would have otherwise.
This is because of complex effects cannabinoids have on the cardiovascular system, including raising resting heart rate, dilating blood vessels, and making the heart pump harder. Research suggests that the risk of heart attack is several times higher in the hour after smoking marijuana than it would be normally."
Benefits of Medical Cannabis
Considering the distribution of cannabinoid receptors in the body, it's no surprise that appropriate dosages can help alleviate problems. Evidence has been increasing for its therapeutic use in the treatment of migraines and headaches, as well as in assisting detoxification and weaning from opioid addiction.26
The NIH has awarded nine research grants totaling $3 million to analyze the potential cannabis may have on pain relief and strengthen the evidence. The studies are focused on the biological activity of natural substances in cannabis that are not psychoactive to steer clear of "THC's disadvantages."
Helene Langevin, director of National Center for Complementary and Integrative Health, spoke out about the need for safe and effective pain relief options, saying:27
"The treatment of chronic pain has relied heavily on opioids, despite their potential for addiction and overdose and the fact that they often don't work well when used on a long-term basis. There's an urgent need for more effective and safer options."
It's important to note that specific strains influence the ratios of phytochemicals, cannabinoids and terpenes, which is a crucial consideration. Results from one study led by researchers from the University of Massachusetts and the University of Bath confirmed the scientific basis for the use of cannabinoids in alleviating gut problems, specifically inflammatory bowel disease.28
Some people are uncomfortable with the use of medical cannabis or the idea of legalizing it. I urge you to evaluate the research and how doctors are using it in clinical practice. You'll find more information about the impact it has on gut health, on your overall health and dozens of cited studies in these past articles:
- Medical Cannabis Offers New Hope for Those With Inflammatory Bowel Diseases
- Cannabis in Modern Medicine
- Can Cannabis Fight Tumors?
- Cannabis: A Lost History

from Articles https://ift.tt/30lfJ3w
via IFTTT
Wearable brain scanner technology expanded for whole head imaging
A new type of wearable brain scanner is revealing new possibilities for understanding and diagnosing mental illness after the technology has been expanded to scan the whole brain with millimeter accuracy.
from Top Health News -- ScienceDaily https://ift.tt/2XE902O
from Top Health News -- ScienceDaily https://ift.tt/2XE902O
Researchers help bring biofriendly materials to drug design for neuro disorders
Researchers have found the first indication that carbon quantum dots, a class of nanoparticles, can be utilized to combat neurological disorders.
from Top Health News -- ScienceDaily https://ift.tt/2MA0dZD
from Top Health News -- ScienceDaily https://ift.tt/2MA0dZD
Memory consolidation during REM sleep
Researchers have found that activity in adult-born neurons (ABNs) in the hippocampus, which is a brain region associated with memory, are responsible for memory consolidation during REM sleep. Identifying the role of specific neurons in memory function deepens our understanding of how memories are formed, retrieved, and consolidated.
from Top Health News -- ScienceDaily https://ift.tt/2MzS3jM
from Top Health News -- ScienceDaily https://ift.tt/2MzS3jM
MKRdezign
Powered by Blogger.