Health, Fitness,Dite plan, health tips,athletic club,crunch fitness,fitness studio,lose weight,fitness world,mens health,aerobic,personal trainer,lifetime fitness,nutrition,workout,fitness first,weight loss,how to lose weight,exercise,24 hour fitness,

Latest Post

As the world deals with the scope of the COVID-19 pandemic, scientific articles have zeroed in on who is most vulnerable to the virus. It appears those who are elderly, overweight and suffer from an underlying health condition like diabetes or high blood pressure are most at risk. But the consumption of ultraprocessed food is increasingly seen as a risk factor for contracting COVID-19, too.

Ultraprocessed foods increase the risk of conditions like obesity, cancer, Type 2 diabetes, cardiovascular disease and gallstones, which make you more vulnerable to illnesses like COVID-19. In fact, eating over four servings of ultraprocessed foods daily increased the risk of premature death by 62% in a 2019 study.1

When it comes to fighting off COVID-19, ultraprocessed foods pose another health danger: They compromise the gut microbiome, which has a crucial role in your body’s immune response to infection and in maintaining overall health. Even before the virus that causes COVID-19 surfaced, ultraprocessed foods were a bad idea but during the current pandemic they are especially dangerous.

Beware of Ultraprocessed Foods

What are ultraprocessed foods, sometimes referred to as UPFs? According to the NOVA Food Classification system, designed by the Center for Epidemiological Studies in Health and Nutrition, they are:2

"[I]ndustrial formulations made entirely or mostly from substances extracted from foods (oils, fats, sugar, starch, and proteins), derived from food constituents (hydrogenated fats and modified starch), or synthesized in laboratories from food substrates or other organic sources (flavor enhancers, colors, and several food additives used to make the product hyper-palatable).

Manufacturing techniques include extrusion, moulding, and preprocessing by means of frying. Beverages may be ultra-processed."

Ultraprocessed foods, aggressively marketed by giant food producers for their profitable potential, constitute around 25% to 60% of daily energy intake in many countries, according to Science Daily. They include:3

"… packaged baked goods and snacks, fizzy drinks, sugary cereals, ready meals containing food additives, dehydrated vegetable soups, and reconstituted meat and fish products — often containing high levels of added sugar, fat, and/or salt, but lacking in vitamins and fiber."

While it is tempting to dismiss the dangers of UPFs by saying that all foods, to some extent, are "processed," food writer Bee Wilson says that is not the case:4

"UPFs are different. They are processed in ways that go far beyond cooking or fermentation, and they may also come plastered with health claims. Bettina Elias Siegel the author of Kid Food: The Challenge of Feeding Children in a Highly Processed World … 'there’s a huge difference between a cooked carrot and a bag of industrially produced, carrot-flavoured veggie puffs' …"

Moreover, cautions Wilson, food giants deliberately mislead consumers. When fat was misleadingly considered the cause of obesity, she says, the food industry rolled out low-fat products. When sugar became the culprit, food giants manipulatively marketed artificially sweetened drinks.5

UPF manufacturers have also launched successful campaigns to convince the public that obesity is not caused by their products, but by lack of exercise. Coca-Cola is among them, and, toward that end, has provided funding to universities and a wide spectrum of medical groups including the American Heart Association, the American Lung Association, the American College of Cardiology and the American Academy of Pediatrics.6

You can't help but wonder if that is why Harvard Medical School/Partners in Health, a recipient of Coca-Cola funding, writes this about obesity:7

"Obesity results from energy imbalance: too many calories in, too few calories burned. A number of factors influence how many calories (or how much ‘energy’) people burn each day, among them, age, body size, and genes. But the most variable factor — and the most easily modified — is the amount of activity people get each day."

Obesity is increasingly linked to serious cases of COVID-19 that require hospitalization, even among young people, according to The New York Times.8 The reasons are not entirely clear, but abdominal obesity can cause compression of the lungs and diaphragm, which impairs breathing ability.

Other factors that could explain the link between obesity and serious cases of COVID-19 could include pre-existing respiratory conditions, a greater amount of circulating, pro-inflammatory cytokines and low-grade inflammation, which are all correlated with obesity. Almost 80 million Americans — 42 percent of the population — are obese.9

A report released by the Intensive Care National Audit and Research Centre on 196 patients critically ill with COVID-19 found 56 patients had a body mass index (BMI) of 25 to 30, which is classified as overweight.10 Fifty-eight had a BMI of 30 to 40, which indicates obesity, and 13 had a BMI of 40 or higher, which is severely obese. In the study, 71.7% of the critical patients were overweight, obese or severely obese.11

Ultraprocessed Food Impairs the Microbiome

Two studies published by The BMJ in 2019 cast ultraprocessed food as a threat to global public health. In a linked editorial, Australian researchers add that the negative effects of UPFs on the gut microbiome must be explored.12

Science has increasingly revealed the huge effect of diet on the human microbiome and its ability to ward off disease. The more diverse with healthy microorganisms a microbiome is, the better it supports the immune system, according to Tim Spector, professor of genetic epidemiology at King's College in London — especially as COVID-19 has spread all over the world. Writing in The Conversation, Spector says:13

"As well as mounting a response to infectious pathogens like coronavirus, a healthy gut microbiome also helps to prevent potentially dangerous immune over-reactions that damage the lungs and other vital organs. These excessive immune responses can cause respiratory failure and death …

The fine details of the interactions between the gut microbiome and the immune system are not fully understood. But there seems to be a link between the makeup of the microbiome and inflammation — one of the hallmarks of the immune response. Gut bacteria produce many beneficial chemicals."

Fermented foods and probiotics are the best route to optimal microbiome health, if they are traditionally made and unpasteurized. Healthy fermented choices include lassi (an Indian yogurt drink), fermented, grass fed organic milk (kefir), fermented soy or natto and different types of pickled fermentations of cabbage, turnips, eggplant, cucumbers, onions, squash and carrots.

Unless antibiotics are absolutely necessary, they should be avoided and, if avoidance is not possible, counteracted with fermented food and probiotics. Be aware that conventionally-raised meats are also a source of antibiotics because animals are routinely fed the medications. Genetically engineered grains and chlorinated and/or fluoridated water can also destroy gut flora.

UPFs Have Put Millions at Risk for COVID-19

Ultraprocessed food is designed to be sensually appealing, hyperpalatable and habit-forming, thanks to additives, crafty packaging and marketing and "convenience." Yet UPFs fill you up without the vitamins, minerals, live enzymes, micronutrients, healthy fats and high-quality protein your body needs. UPFs increase how fast people eat and delay how "full" they feel, causing obesity and metabolic dysfunction.

Dr. Aseem Malhotra is an honorary consultant cardiologist at Lister Hospital in Stevenage, England.14 According to an article he wrote in European Scientist, UPFs cause:15

"… chronic metabolic disease which can affect many of 'normal' weight. Furthermore, sarcopenic obesity may misclassify many elderly patients to having a normal BMI on hospital admission with COVID-19 … There’s no such thing as a healthy weight, only a healthy person.

A recent commentary In Nature states that 'patients with type 2 diabetes and metabolic syndrome might have to up 10 times greater risk of death when they contract COVID-19' and has called for mandatory glucose and metabolic control of type 2 diabetes patients to improve outcomes."

Kristin Lawless, author of the book, "Formerly Known As Food: How the Industrial Food System Is Changing Our Minds, Bodies, and Culture," also sees correlations between metabolic dysfunction and succumbing to COVID-19:16

"These underlying conditions correlate with increased morbidity and mortality for those who contract the virus. Preliminary findings show that metabolic dysfunction is causing devastating complications from COVID-19 and, shockingly, only 12 percent of the entire U.S. adult population is considered metabolically healthy.

Metabolic dysfunction has one primary source: our highly processed, sugar- laden, nutrient-poor food supply."

While the millions who suffer from metabolic syndrome from UPFs are not seen as urgent like COVID-19 is, the problems are one and the same, according to Malhotra. Governments, in addition to telling people to stay home to save lives during the COVID-19 pandemic, should address diet, he asserts. He writes:17

"[A]n equally strong if not more significant population health message should now be to 'eat real food, protect the NHS and save lives.'

Such implementation backed by policy changes may not just save hundreds and potentially thousands of lives around the world in the coming months but given the high likelihood of another international viral pandemic in the next decade a healthier population … will be much better equipped to handle what would then be a smaller mortality peak on the next occasion."

UPFs Are Especially Harmful to Poor Communities

People living in poverty, whether in developing or advanced countries, are especially vulnerable to health problems from ultraprocessed foods and COVID-19. According to Malhotra:18

"[T]he disproportionate numbers of those from black and ethnic minority backgrounds succumbing to the virus may in part be explained by a significantly increased risk of chronic metabolic disease in these groups."

Even before the COVID-19 pandemic, food giants have targeted those with low incomes with aggressive marketing of UPFs. Following initiatives by Brazil to fight the trend, Ecuador, Uruguay and Peru have urged citizens to avoid UPFs in favor of natural foods.19 Food deserts further the dietary exploitation of the poor, according to Lawless:20

"New data show that Black people are dying at higher rates from COVID-19 than other groups. Certainly lack of health care and poor quality of care shape outcomes, and it is well documented that poverty rates among people of color are significantly higher than in white populations.

Perhaps less obvious is the influence of Big Food’s targeted advertising to people of color in neighborhoods with little access to fresh, whole foods. This means many people of color often rely on fast-food and cheap packaged foods for meals that provide more caloric bang for the buck.

Nationwide, Black people have much higher rates of diet-related diseases — Black adults are 60 percent more likely to be diagnosed with diabetes than white adults."

The USDA defines a food desert as a low-income tract where many residents do not have easy access to a supermarket or large grocery store.21 In addition to a lack of food outlets offering healthy food, residents' lack of transportation to get to stores is a big factor. Residents who have to walk with their groceries or take the bus can carry fewer groceries, and transporting perishable items is especially difficult.

According to the USDA, many types of organizations like businesses, local governments and nonprofits are eligible for assistance to address the problems created by food deserts.22 However, like discouraging the consumption of UPFs, such changes take time and certainly will not occur during the COVID-19 pandemic.

Other Environmental Causes of COVID-19

A diet of UPFs puts people at risk for COVID-19 because of the metabolic, immune system and microbiome degradation it causes. But the coronavirus pandemic also has environmental causes and repercussions, says Lawless:23

"All over the world, industrial agriculture has pushed small-scale farmers deeper into forests where these types of pathogens exist. The decimation of forests has also sent those who bring wild animals into city markets deeper into remote forest areas, resulting in human exposure to novel pathogens.

What’s more, animals confined in factory farms are perfect incubators when these pathogens spill over — unsanitary, cramped conditions among animals with near-identical genetics means that viruses spread rapidly and often become more virulent.”

Whether people whose vulnerability to disease has been increased by Big Agriculture or viruses spread from its excesses, most experts agree we need a radical overhaul of the entire food production and distribution system. According to Lawless:24

"First, our industrial food system is decimating our environment. Second, our nutrient-depleted, and chemically saturated processed food supply is changing our bodies from the inside out …

Large-scale mono-crop farms, concentrated animal feeding operations, fertilizers, pesticides, gas-powered machinery, storage facilities, manufacturing plants, and shipping methods are all dependent on and made possible by fossil fuels … A new Harvard analysis shows that exposure to fine particulate matter correlates with COVID-19 deaths.25

Fuel combustion results in dangerous fine particulate matter, which kills 7 million people prematurely each year worldwide."

If ever there were a time to consider our eating habits and the domination of harmful agricultural systems it is during this coronavirus pandemic.


from Articles https://ift.tt/2ScmY99
via IFTTT

During the COVID-19 pandemic, many are asking how they can strengthen their immune system to reduce the potential of getting sick, and how they can support their body if they have a viral infection. As Dr. Roger Seheult explains in this video, natural killer cells are part of your immune response.

While there is no known drug or medication that kills a virus, there are nutraceuticals that have an effect on them. Some of the nutraceuticals support your immune system, while others have the ability to reduce your viral load, as discussed by Mark McCarty and James DiNicolantonio.1

Solar ultraviolet-B radiation2 and supplemental vitamin D3 have also been shown to reduce pandemic fatality rates; this makes sense considering how important vitamin D is for controlling infections and lowering your risk for influenza and the common cold.

How Your Body Uses Natural Killer Cells

Natural killer cells are part of a larger group of cells called lymphocytes. These play a key role in your immune response and defense against viral infections. Inside the cytoplasm of natural killer cells are lytic granules,4 such as granulysin, perforin and granusyme A and B.5

Natural killer cells work by recognizing stressed cells and then using cytotoxic abilities to kill the abnormal cell.6 Once recognized, natural killer cells secrete the granules into a synapse delivering the granules to a target cell. These then trigger apoptosis in the infected cell.

Defects in this system are related to fatal diseases,7 such as Griscelli syndrome type 2.8 This rare, inherited condition affects the immune system, leaving individuals prone to recurrent infections.

Natural killer cells control infection by limiting tissue damage and spread and they help control tumor growth by limiting the spread of abnormal cells.9 They also regulate cells engaged with macrophages, T cells and endothelial cells. Additionally, they can mediate the immune response.

As Seheult explains in the video, natural killer cells are part of the innate immune system, which is the first line of defense against pathogens.10 The next step is adaptive immunity, also called acquired immunity. This response is specific to the pathogen that enters your body. When you build up an immunity to a pathogen, it is the function of your adaptive immune response.

A Forest Walk May Boost Your Body’s Ability to Fight Viruses

Scientific evidence shows that walking in a forest, also called forest bathing, can help enhance your natural killer cell activity, including the number of cells and the length of activity. Research has been done in men and women involving field trips to the forest. In this first study,11 researchers engaged 12 healthy men who normally worked at large companies in Tokyo.

The participants were taken on a three-day, two-night trip to three different forests. On the first day, they walked for two hours; on the second day they walked for two hours both in the morning and afternoon; and on the third day they left for home. Blood was drawn in the morning before any intervention and after the first and second days of walking.

The study team analyzed natural killer cell activity and the proportion of lytic granules and natural killer cells. On the last day, 11 out of 12 of the subjects had 50% higher activity compared to their levels before entering the forest. The researchers believed:12

“Taken together, these findings indicate that a forest bathing trip can increase NK activity, and that this effect at least partially mediated by increasing the number of NK cells and by the induction of intracellular anti-cancer proteins.”

Later, the same team performed the same intervention on 13 healthy women.13 Blood and urine samples were also collected seven days and 30 days after the trip was completed. The team also measured concentrations of phytoncides in the forest, which are airborne chemicals emitted by the plants.

The results of this study showed natural killer cell activity remained raised for more than seven days, as did the number of natural killer cells and the “levels of intracellular anticancer proteins.”

The team questioned whether the effects on the natural killer cells was representative of being outdoors, due to exercise or related to the trees. They designed and executed another study14 with two groups of men who visited two different forests or a city for three days and two nights.

The intervention was the same with blood drawn and urine samples collected before the study began, each day and on Days 7 and 30 after the intervention was complete. During this study they also measured the phytoncides in the forest and the city. As you might expect, measurements in the forest were high, but in the city, most levels were so low they couldn’t be measured. The researchers concluded:15

“The present study confirmed that a forest bathing trip enhances the immune response as measured by human NK activity and the numbers of NK cells, as reported previously. In contrast, a trip to places without forests (city tourist visit) had no effect on NK activity or the numbers of NK cells, indicating that forest bathing does indeed enhance human NK activity.

Moreover, we also found that the increased NK activity and numbers of NK cells induced by a forest bathing trip lasted more than 7 days, even 30 days, after the trip. This suggests that if people visit a forest once a month, they may be able to maintain increased NK activity. This may be important in health promotion and preventive medicine.”

Can You Repeat These Results at Home?

Once the researchers had identified phytoncides as the probable reason individuals were experiencing a higher measure of natural killer cell activity, they designed a follow-up study.16 In this they attempted to recreate the boost in natural killer cells using essential oils from trees.

They engaged 12 healthy men who stayed in a city hotel for three nights between 7 p.m. and 8 a.m. In the morning they returned to work in the city. During the night, researchers ran a humidifier with stem oil from the hinoki cypress tree. “Blood samples were taken on the last day and urine samples were analyzed every day during the stay,” they reported.

Phytoncide measurements in the room were also taken. The study team found there was a statistically significant jump in natural killer cell activity after sleeping in the hotel room, despite the fact they returned to work in the city each day. Urine was analyzed for adrenaline and noradrenaline, since the presence of adrenaline reduces the number of natural killer cells.

Although there was a statistically significant difference in the measurement of adrenaline in the urine of those who stayed in the forest,17 the same difference did not occur in all who stayed in a hotel with stem oil diffused in the room.18

When the data were analyzed together, there wasn’t a statistically significant drop in the excretion of adrenaline in the urine. However, when the researchers separated the samples into those where the adrenaline increased and those where it decreased, there was a statistically significant difference in the reduction of adrenaline in the urine.

They concluded that, while there was beneficial activity to short-term exposure, prospective studies in people exposed to phytoncides long-term would be needed to confirm the effect.

You Also Benefit From Green Spaces

If you don't have a local forest, you can still benefit from exposure to green spaces. In one meta-analysis of 143 studies,19 scientists noted statistically significant reductions in blood pressure, heart rates and levels of cortisol secretion measured in saliva. They also identified decreased incidences of diabetes and all-cause and cardiovascular mortality.

The researchers from the University of East Anglia20 analyzed studies looking at postoperative recovery time. In all, there were 290 million participants across all 143 studies from 20 different countries.

When they correlated the amount of time individuals had spent in green areas with 100 health measurements, they also found that women who were pregnant had a reduced risk for preterm birth and a lower risk of delivering a baby who was small for gestational age.

The relationship may be related to a higher level of physical activity that often comes in green spaces. It could also have something to do with social interaction or greater exposure to sunlight. The researchers concluded:21

“Green prescriptions involving greenspace use may have substantial benefits. Our findings should encourage practitioners and policymakers to give due regard to how they can create, maintain, and improve existing accessible greenspaces in deprived areas.”

Develop Habits to Support Your Immune System

Developing healthy habits is important to support your immune system, reduce the potential for viral infections and lower your risk of chronic disease. While there are multiple choices you make each day, the following factors are foundational to creating a strong health plan.

• Gut microbiome — Your gut microbiota is key to your immune system and digestive health. Fermented food and fiber are vital to repopulating your gut with beneficial bacteria and providing the necessary nutrients for them to thrive.

• Exercise — Research evidence underscores the benefits of exercise to your immune health. Seek to raise your heart and breathing rate for 30 minutes each day in addition to moving out of your chair frequently. Your body requires both exercise and movement to stay healthy.

• Sleep — The quality and quantity of your sleep has a regulatory effect on your immune system.22 Developing good sleep habits requires just a little effort. If you struggle with getting to sleep or staying asleep, consider the tips I share in “Top 33 Tips to Optimize Your Sleep Routine.”

• Vitamin D — This is another powerful component to supporting your immune system and the prevention and treatment of viral infections, including COVID-19. To read more about maintaining appropriate levels and how it may help reduce your risk of COVID-19, see “Vitamins C and D Finally Adopted as Coronavirus Treatment.”


from Articles https://ift.tt/2KKRQJL
via IFTTT

A curious thing is happening amid the COVID-19 pandemic: As COVID-19 cases and deaths mount, hospital admissions for other acute ailments are markedly dropping.

In an April 6, 2020, New York Times article, Dr. Harlan Krumholz — professor of medicine at Yale and director of the Yale New Haven Hospital Center for Outcomes Research and Evaluation — notes:1

“The hospitals are eerily quiet, except for Covid-19. I have heard this sentiment from fellow doctors across the United States and in many other countries. We are all asking: Where are all the patients with heart attacks and stroke? They are missing from our hospitals.

Yale New Haven Hospital, where I work, has almost 300 people stricken with Covid-19, and the numbers keep rising — and yet we are not yet at capacity because of a marked decline in our usual types of patients.

In more normal times, we never have so many empty beds … What is striking is that many of the emergencies have disappeared.”

Drastic Reduction in Emergency Admissions

In an informal Twitter poll, created by Angioplasty.org, an online community of cardiologists, 45.4% reported a 40% to 60% reduction in hospital admissions related to heart attacks, and 22.4% reported a reduction greater than 60%.2 Other emergencies, including acute appendicitis and gallbladder disease have also dropped, according to unofficial reports from medical professionals.3 What’s more, according to Krumholz:4

“This is not a phenomenon specific to the United States. Investigators from Spain reported a 40 percent reduction in emergency procedures for heart attacks during the last week of March compared with the period just before the pandemic hit.”

We still do not have an explanation for these statistics. Krumholz hypothesizes that patients may be avoiding face-to-face medical care for fear of contracting COVID-19. If this is the case, their condition may significantly worsen, and lives may be unnecessarily lost.

“As we fight coronavirus, we need to combat perceptions that everyone else must stay away from the hospital. The pandemic toll will be much worse if it leads people to avoid care for life-threatening, yet treatable, conditions like heart attacks and strokes,” Krumholz says.

This isn’t the only possibility, however. As Krumholz notes, natural triggers of heart attacks and strokes may simply have been removed by the imposed social distancing, eating at home and having more time for physical activity.

He’s not convinced that this theory is the most likely explanation, though, considering respiratory infections tend to increase the risk of heart attack. The fear and stress of the situation should theoretically also have led to an increase in heart attacks, as depression, anxiety and frustration “are all associated with a doubling or more of heart attack risks.”5

Delaying Necessary Care Could Cost You

The same story is also reported in an April 19, 2020, article6 in The Washington Post, which notes that:

“Five weeks into a nationwide coronavirus lockdown, many doctors believe the pandemic has produced a silent sub-epidemic of people who need care at hospitals but dare not come in.

They include people with inflamed appendixes, infected gall bladders and bowel obstructions, and more ominously, chest pains and stroke symptoms, according to these physicians and early research …

At [the Medical University of South Carolina, trauma medical director Dr. Evert] Eriksson’s general surgery floor, which has 20 beds, housed as few as three people for two to three weeks, he said. Now the census is back over 20.

‘What we’re seeing is late presentation,’ he said. ‘I would say 70 percent of the appendicitis on my service right now are late presentations. What happens when you present late with appendicitis is we can’t operate on you safely.’”

All-Cause Mortality Is Still Uncertain

Whatever the reason for the drastic decreases in hospital admissions for ailments other than COVID-19, time will tell whether the decrease has actually resulted in increased all-cause mortality or not. As reported by The Washington Post:7

“Much of the reporting about missing patients is anecdotal — in medical chat rooms and on doctors’ social media accounts. Doctors say it’s unlikely there has been a decline in most of these conditions, which suggests that at least a few people may be dying at home, although there is no data yet to corroborate that.”

Some do claim all-cause mortality has risen during this pandemic. According to an April 14 report by The New York Times:8

“Three thousand more people died in New York City between March 11 and April 13 than would have been expected during the same time period in an ordinary year, Dr. Oxiris Barbot, the commissioner of the city Health Department, said in an interview.

While these so-called excess deaths were not explicitly linked to the virus, they might not have happened had the outbreak not occurred, in part because it overwhelmed the normal health care system.”

The New York Times’ claim that the deaths occurred as a result of COVID-19 “overwhelming the health care system” seems suspect, however, in light of so many doctors saying their hospitals are nowhere near capacity.

These conflicting reports show just how difficult it is to tease out the truth without proper data collection and distribution. Without accurate and complete data, it’s virtually impossible to draw any definitive conclusions.

Is Mortality Actually Going Down?

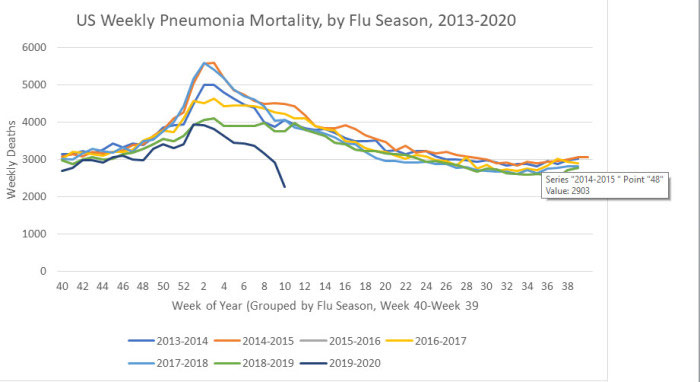
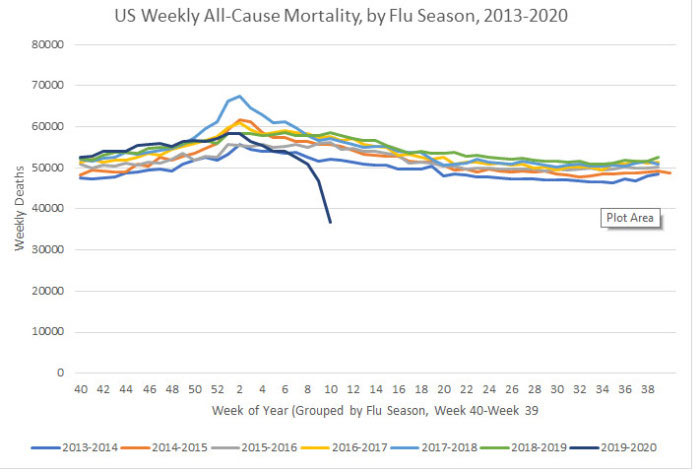
Two interesting graphs created by I. Ratel9 — who freely admits he’s not a statistician or doctor but has degrees in industrial management and automotive technology and whose interest in this is fueled by the fact that he’s immunocompromised — suggest a downturn in both pneumonia deaths and all-cause mortality.

Although final data won’t be released until 2021, I did find in my own research that pneumonia deaths in the current flu season (2019-20) are down compared to 2018-19,10 so I’m including Ratel’s calculations here for anyone interested in diving deeper into his data gathering. Ratel explains the graphs:11

“I’ve been watching CDC’s flu surveillance since last fall when there were rumors floating about of a nasty new flu bug in China … According to the South China Post the first COVID-19 case in Hubei province China was found November 17. Even that article states that patient zero may have been earlier than that …

I contend that it is reasonable to believe that the SARS-CoV-2 virus began circulating around the global population back in November and December, spreading not only across China, but to much of the world.

When considering that possibility, patterns in CDC’s regular ILI (Influenza Like Illness) surveillance data become interesting. I’ve taken their data, and applied my meager Excel skills to chart out some things …

Prior to January we weren’t looking for this virus. We’ve only had useful testing capability for a few weeks now. Given the information we have on disease progression, I assumed that there would be an upward trend in Pneumonia mortality as without looking for and testing for SARS-COV-2, victims should have been classified as deaths due to pneumonia. So, I charted it, with the last 6 years of data published by CDC.

CDC calls week 40 of a year the beginning of the flu season, so all my charts are set to begin in week 40 of one year and end in week 39 of the next, showing years as flu seasons.

US weekly pneumonia mortality

There is the customary increase at week 1, I assume related to holiday festivities and travel. However the 2019-2020 season shows week by week pneumonia mortality to be low compared to the last few years … [and a] sharp decline over the last few weeks.

I next looked at all-cause mortality. Perhaps COVID-19 deaths hadn’t been captured in the pneumonia data … We see here that all-cause mortality ran on the high side of normal until it started to drop at the beginning of 2020, and recently dropped significantly. Again, no indication of this virus killing people beyond seasonal norms,” Ratel writes.

US weekly all cause mortality

Avoiding Hospitals Might Lower Death Toll

That said, previous research has shown that when conventional medical intervention is reduced, mortality often goes down. For example, back in 2000, all-cause mortality in Israel dropped during a time when Israeli doctors at public hospitals went on strike.12

One of the reasons for this is because medical care itself tends to be a risky business. Research13 published in 2014 found nearly 1 in 5 elderly Medicare patients are injured by their medical care. The most common medical injuries included receiving the wrong medication, having an allergic reaction to medication given, and receiving treatment that led to more complications. As a result of these injuries, they also had a death rate nearly double those who were not injured by their care.

Other research14 published in 2013 concluded 210,000 Americans are killed by preventable hospital errors each year, and when deaths related to diagnostic errors, errors of omission, and failure to follow guidelines were included, the number skyrocketed to an estimated 440,000 preventable hospital deaths each year.

One in 25 patients in the U.S. also contracts some form of infection while hospitalized, and an estimated 205 Americans die from hospital-acquired infections every day. The unfortunate truth is that once you’re hospitalized, you’re immediately at risk for medical errors that might cost you your life. That’s not to say you should never go to the hospital, though.

If you suspect you’re having a heart attack, stroke or appendicitis, for example, you should seek immediate care. Many other ailments that people seek treatment for, however, may simply place them at increased risk for complications.

The difficulty is determining what you might be able to address at home and what’s an actual emergency. If you have access to a holistic physician you trust, calling them for a consultation would be a good idea.

COVID-19 Deaths Jump Due to Reclassification

While other ailments appear to have declined (at least based on hospital admission rates, which may present a false picture of the situation), COVID-19 deaths in the U.S. have undergone a sudden jump mid-April.

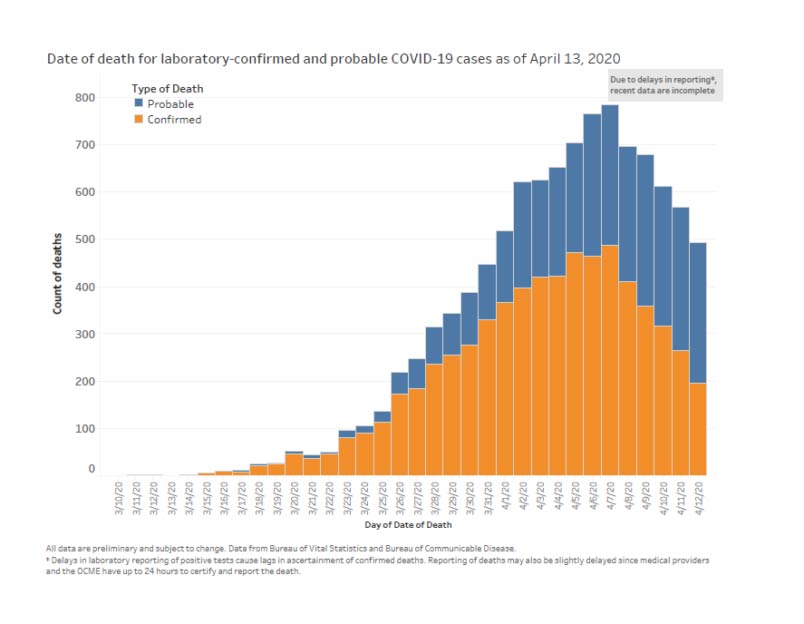
While some use this as a sign that the infection is spreading and perhaps more lethal than suspected, the real reason for this sudden jump is simply the reclassification of COVID-19 deaths to include “probable” cases.

While the U.S. Centers for Disease Control and Prevention15 separates confirmed COVID-19 deaths from all-cause mortality, pneumonia deaths, influenza deaths and deaths with both pneumonia and COVID-19, it has issued guidance to states on how to document COVID-19 deaths on death certificates, indicating that COVID-19 should be indicated if “the disease caused or is assumed to have caused or contributed to death.”16

By not requiring COVID-19 deaths to be laboratory confirmed, the death rate can easily become skewed. New York City has officially transitioned its record keeping to include suspected COVID-19 cases,17,18 and as you’d expect, when suspected or “probable” deaths are counted without any proof that SARS-CoV-2 infection was involved at all, the numbers dramatically increase. Ultimately, there is no way to tell what the real impact of the pandemic actually is when using this system.

Looking at the data19 collected for NYC between March 11, 2020, and April 13, 2020, 23.5% of deaths involving residents between the ages of 45 and 64 are in the “probable” category, as are 23.6% of those among 65- to 74-year-olds and 49.9% of those over the age of 75.

As noted by The New York Times20 on April 14, 2020, New York City’s addition of thousands of “probable” cases increased the alleged death rate from COVID-19 by 17% overnight.

day of date of death

Signs of Suicide Epidemic Emerge

Whether all-cause mortality is in fact going up or down, as predicted we are now starting to see a rise in suicides. Suicide statistics reliably follow economic trends, with financial downturns triggering higher rates of depression and despair. According to an updated March 27, 2020, report by The Sacramento Bee:21

“FirstLink, a company that answers both 211 helplines and the National Suicide Prevention Lifeline for North Dakota and parts of Minnesota said this week that call volume in some of its call centers is up 300%.”

According to a spokeswoman for the national Crisis Text Line, text conversations were double that of the normal volume during the week of March 15.22 Google also reports that searches for “panic attack symptoms” have doubled compared to last year.23

The CDC, meanwhile, appears to take things in stride, noting that “Fear and anxiety about a disease can be overwhelming and cause strong emotions in adults and children,” but that “Coping with stress will make you, the people you care about, and your community stronger.”24

While true as a general statement, the current pandemic has delivered a perfect storm of challenges that is sure to bring many to a breaking point. We’re not just talking about fearing a disease. We’re also talking about the very real challenges of keeping a roof over our heads and feeding ourselves and our families when the entire country has been shut down and millions of workers have been laid off.

According to reports by The Federalist25 and Red State,26 suicides exceeded COVID-19 deaths in Tennessee the week of March 20. The Regional Forensic Center in Tennessee was investigating nine suicides as of March 27, eight of which took place in Knox County — one of the few areas in Tennessee where businesses were ordered to close.

The suicides, which occurred within a 48-hour period, account for 10% of the 2019 suicide rate for the region.27 Meanwhile, only six patients died from COVID-19 in the entire state that week. In a statement, Knoxville, Tennessee Mayor Glenn Jacobs said:28

“That number is completely shocking and makes me wonder if what we are doing now is really the best approach. We have to determine how we can respond to COVID-19 in a way that keeps our economy intact, keeps people employed and empowers them with a feeling of hope and optimism — not desperation and despair.”

Similar warning signs are starting to be noted in other states as well, including Oregon. In a March 24 local news report,29 Portland police chief Jami Resch said suicide threats or attempts are 41% higher now than this time last year, and there’s been a 23% increase since the 10 days before a state of emergency was declared in Portland.

Unfortunately, this is likely the beginning of what is most certainly only going to worsen with time, as many financial experts are predicting a depression worse than the Great Depression of the 1930s.30

Suicide Prevention Resources

Clearly, we’re facing an unprecedented challenge, and it’s hard to know exactly what the right thing to do is. There are risks and benefits to every choice. However, I’ve argued since the very beginning that ignoring the human cost of economic collapse is a serious mistake. It’s an equally serious mistake to spread fear unless fear is truly warranted. Mainstream media have a lot to answer for in this regard.

While the future is certainly unsure, I urge you to do what you can to keep yourself on an even keel going forward. Do your best to moderate your fears. And, if you need help, don’t hesitate to reach out to family, friends or any of the available suicide prevention services:

  • The National Suicide Prevention Lifeline (U.S.) — Call 1-800-273-TALK (8255)
  • Crisis Text Line — Text HOME to 741741 to connect with a crisis counselor
  • Lifeline Crisis Chat — Chat online with a specialist who can provide emotional support, crisis intervention and suicide prevention services at www.crisischat.org


from Articles https://ift.tt/2KIrI27
via IFTTT

Researchers have recreated how toxins from smoking cause unique patterns of DNA damage. The discovery could help scientists better understand the cause of bladder cancer and the link to smoking. The causes of bladder cancer remain largely unknown, however smoking is seen as the main risk factor for the disease.

from Top Health News -- ScienceDaily https://ift.tt/2Yeg4nv

MKRdezign

Contact Form

Name

Email *

Message *

Powered by Blogger.
Javascript DisablePlease Enable Javascript To See All Widget