Health, Fitness,Dite plan, health tips,athletic club,crunch fitness,fitness studio,lose weight,fitness world,mens health,aerobic,personal trainer,lifetime fitness,nutrition,workout,fitness first,weight loss,how to lose weight,exercise,24 hour fitness,

Latest Post

A June 2021 study using high resistance Inspiratory Muscle Strength Training (IMST) demonstrated a reduction in blood pressure measurements as well as aerobic exercise or medication.1 High blood pressure, which is also called hypertension, is one of the most prevalent health conditions in the U.S. It is estimated that 47.3% of U.S. adults, or 116 million people, have high blood pressure.2

High blood pressure can increase your risk of a heart attack and stroke. The American Heart Association reported that the death rate from this condition increased nearly 11% from 2005 to 2015.3 Despite advances in education, screening and treatment, cardiovascular disease remains the leading cause of death in the world, claiming the lives of 659,041 people in the U.S. in 2019 (latest data available).4

The American Heart Association5 recommends making lifestyle changes that include changing your diet, monitoring your blood pressure, limiting alcohol, maintaining a healthy weight and getting exercise.

When these measures do not reduce your blood pressure to within normal limits the standard recommendation is high blood pressure medications.6 The types of medication can include diuretics, beta blockers, ACE inhibitors and calcium channel blockers — which may be prescribed individually or in a combination as determined by your doctor. Each comes with a list of possible side effects that may include weakness, fatigue, a loss of taste and swollen feet and ankles.7

If you have high blood pressure or would like to help reduce your risk of getting high blood pressure, the results of this recent study are encouraging. There are additional strategies you can use that I discuss below.

Breathing This Way May Lower Blood Pressure as Well as Drugs

The current study8 is the strongest evidence presented yet that IMST may play a role in reducing blood pressure, thus reducing the risks of cardiovascular disease. Although aerobic exercise is one foundational strategy for controlling blood pressure, fewer than 40% meet the current recommended guidelines.9

Lead author Daniel Craighead is an assistant research professor in the department of Integrative Physiology. Researchers were seeking a time efficient way of helping to reduce blood pressure, since more than 60% of people were not meeting exercise guidelines. Craighead commented in a press release:10

"There are a lot of lifestyle strategies that we know can help people maintain cardiovascular health as they age. But the reality is, they take a lot of time and effort and can be expensive and hard for some people to access. IMST can be done in five minutes in your own home while you watch TV.

We found that not only is it more time-efficient than traditional exercise programs, the benefits may be longer lasting.”

IMST was originally developed for critically ill patients with respiratory diseases to help improve the strength of their inspiratory muscles. The strategy uses a handheld device that provides resistance to the user as they inhale vigorously, thus strengthening muscles.

Initially, physicians recommended a 30-minute program each day with a low level of resistance. However, recent tests using high resistance six days a week were initiated to determine if the participant would reap the same benefits with respiratory, cardiovascular and cognitive improvements.

In the most recent study researchers engaged 36 adults ages 50 to 79 who had above normal systolic blood pressure. Half the participants used high resistance IMST and half used lower resistance IMST for six weeks. At the end of the intervention the group using high resistance IMST experienced a nine-point reduction in their systolic blood pressure.11

Respiratory Conditioning May Benefit Cognitive Function

Six weeks after stopping the program, the group maintained most of their improvement. Additionally, the researchers measured a 45% improvement in vascular endothelial function, an increase in the level of nitric oxide and a reduction in markers of oxidative stress and inflammation. The researchers were encouraged by the compliance rate in the group as they completed 95% of the sessions.

Senior author of the study, Doug Seals, is a distinguished professor of integrative physiology. In his past research, data demonstrated that postmenopausal women don't get as much benefit from aerobic exercise as men do. However, in the current study, IMST improved markers in postmenopausal women as much as in men. “That’s noteworthy,” Seals said.

Preliminary results also suggest that it improves some cognitive function and physical fitness. The researchers are unable to explain how using IMST can lower blood pressure, but they postulate it has something to do with raising the level of nitric oxide. Craighead uses IMST in his marathon training. He says:12

"If you're running a marathon, your respiratory muscles get tired and begin to steal blood from your skeletal muscles. The idea is that if you build up endurance of those respiratory muscles, that won't happen and your legs won't get as fatigued. It's easy to do, it doesn't take long, and we think it has a lot of potential to help a lot of people.”

There are some physiological conditions that contraindicate IMST,13 including a history of spontaneous pneumothorax, a pneumothorax related to a traumatic injury that isn’t healed and a ruptured eardrum that is not fully healed.

Some asthma patients with unstable disease or individuals with abnormally low perception of dyspnea may also be unsuitable candidates. Researchers encourage people who want to consider trying IMST to first consult with their health care provider.14

What Does Blood Pressure Measure?

Your blood pressure measurement is an indication of how much pressure exists within your arterial system. As blood moves through your arteries, it places pressure along the walls of the vessels.

Your systolic blood pressure is the pressure exerted on the arteries when the heart beats and is the top number in the measurement. Your diastolic blood pressure is the pressure in the blood vessels as the heart muscle relaxes between beats.

The systolic blood pressure is always higher than the diastolic blood pressure. Blood pressure measurements are given in units of millimeters of mercury (mm Hg). In 2017, the American Heart Association and the American College of Cardiology,15 in collaboration with nine other health organizations,16 developed new guidelines lowering the systolic and diastolic blood pressure numbers for the diagnosis of high blood pressure.

Previously, elevated blood pressure started at 140/90 for people younger than age 65 and 150/80 for people 65 and older.17 The new guidelines were created to help address high blood pressure earlier and thus hopefully reduce the risk of heart attack and stroke. There are five categories of blood pressure measurements that are recognized by the American Heart Association.18

  • Normal blood pressure is consistently 120/80 or less
  • Elevated blood pressure is consistently 120-129/80
  • Hypertension Stage 1 is blood pressure that is consistently 130-139/80-89
  • Hypertension Stage 2 is blood pressure that is consistently 140/90 or greater

A hypertensive crisis occurs when blood pressure readings are suddenly 180/120 or greater, which may trigger organ damage with symptoms that include chest pain, shortness of breath, changes in vision or difficulty speaking. It is crucial you seek emergency medical treatment immediately.

Risks Associated With High Blood Pressure

There are multiple risks associated with chronic high blood pressure. These include kidney disease and kidney failure, heart attack, stroke, vision loss, heart failure and sexual dysfunction.19

High blood pressure also increases your risk for peripheral artery disease (PAD). This occurs when the arteries in your extremities, stomach or head become narrowed. It causes pain and fatigue when the arteries cannot deliver enough oxygen to the muscles.20 Another recent risk factor of high blood pressure is the increased risk of death with COVID-19.

If high blood pressure is allowed to continue it can also lead to vascular dementia.21 In one study,22 researchers found that older adults who had a consistently elevated average systolic blood pressure had a greater risk for brain lesions and tangles associated with Alzheimer's disease. In this study, the average pressure in the senior adults was 134/71. As reported in the press release:23

“Researchers found that the risk of brain lesions was higher in people with higher average systolic blood pressure across the years. For a person with one standard deviation above the average systolic blood pressure, for example 147 mmHg versus 134 mmHg, there was a 46 percent increased risk of having one or more brain lesions, specifically infarcts.

For comparison, the effect of an increase by one standard deviation on the risk of having one or more brain infarcts was the equivalent of nine years of brain aging.”

This Also Raises Nitric Oxide to Relax Blood Vessels

Researchers in the current study postulated that one of the reasons the breathing exercise helps reduce blood pressure may be because it helps release nitric oxide into the arterial system. Another way to get nitric oxide naturally is using a simple and quick exercise developed by Dr. Zach Bush.

The exercise is called the Nitric Oxide Dump and is an efficient anaerobic activity that works better the more you do it. I demonstrate a version of that work out in the video above. The routine works best if you complete it three times a day and wait at least 2 hours between each session.

This allows nitric oxide to be synthesized so it can be released. Benefits to naturally releasing nitric oxide include relaxing your arterial system and potentially lowering blood pressure, improving age-related decline in muscle mitochondria and reducing insulin resistance.

For further explanation of the many benefits behind releasing nitric oxide naturally, see “Fitness Checkup: Why You Need to Try the Nitric Oxide Dump Workout.”

These Strategies May Also Help Lower Blood Pressure

In addition to strategies you can use to reduce your blood pressure, it's important to note one study24 published in the Journal of the American College of Cardiology demonstrated there are differences between taking a central aortic blood pressure, which is an invasive procedure, and a peripheral blood pressure using a cuff on your arm or leg.

To reduce the potential inaccuracies in taking a peripheral blood pressure, several factors must be taken into consideration. These include the size of the cuff and relationship to your arm, the placement of the blood pressure cuff, your body position and activity during blood pressure reading and nicotine, caffeine or alcohol intake prior to having your blood pressure measured.

You’ll find further explanations and ways to reduce potential inaccuracies in “Blood Pressure Testing Is Mostly Inaccurate.” You must also take care to reduce the effect of identified factors that contribute to high blood pressure. These include insulin and leptin resistance,25 elevated uric acid levels,26 lead exposure27 and air28 and sound pollution.29 Below are several additional lifestyle strategies that can help lower your blood pressure naturally.

Optimize your vitamin D level — Vitamin D deficiency is associated with both arterial stiffness and hypertension.30 For optimal health, maintain a vitamin D level between 60 and 80 nanograms per milliliter year-round.

Mind your sodium-to-potassium ratio — According to Dr. Lawrence Appel,31 lead researcher on the DASH diet and director of the Welch Center for Prevention, Epidemiology and Clinical Research at Johns Hopkins, your diet as a whole is the key to controlling hypertension — not salt reduction alone. He believes a major part of the equation is this balance of minerals — i.e., most people need less sodium and more potassium, calcium and magnesium.

Consider intermittent fasting — Intermittent fasting is one of the most effective ways I've found to normalize your insulin/leptin sensitivity, which is a root cause of hypertension.

Exercise regularly — A comprehensive fitness program can go a long way toward regaining your insulin sensitivity and normalizing your blood pressure. If you are insulin resistant, you'll also want to include weight training. When you work individual muscle groups, you increase blood flow to those muscles, and good blood flow will increase your insulin sensitivity.

Walk barefoot — Going barefoot will help you ground to the earth. Experiments show that walking barefoot outside (also referred to as Earthing or grounding) improves blood viscosity and blood flow, which help regulate blood pressure. So, do yourself a favor and ditch your shoes now and then.

Grounding also calms your sympathetic nervous system, which supports your heart rate variability. This in turn promotes homeostasis, or balance, in your autonomic nervous system. In essence, anytime you improve heart rate variability, you're improving your entire body and all of its functions.

Address your stress — The connection between stress and hypertension is well documented, yet still does not receive the emphasis it deserves. Suppressed negative emotions such as fear, anger and sadness can severely limit your ability to cope with the unavoidable everyday stresses of life. It's not the stressful events themselves that are harmful, but your lack of ability to cope.

The good news is, strategies exist to quickly and effectively transform your suppressed, negative emotions, and relieve stress. My preferred method is the Emotional Freedom Techniques (EFT), an easy to learn, easy to use technique for releasing negative emotions. EFT combines visualization with calm, relaxed breathing, while employing gentle tapping to "reprogram" deeply seated emotional patterns.

Essential oils — Several essential oils can also be helpful, including lavender, ylang-ylang, marjoram, bergamot, rose, frankincense, rosemary, lemon balm and clary sage. In one study,32 scientists found exposure to essential oil for one hour effectively reduced stress as measured by a reduction in the participants' heart rate and blood pressure.

The effect was only temporary, however. In another, similar study,33 inhalation of a blend of lavender, ylang-ylang, neroli and marjoram essential oils was associated with a reduction in blood pressure and cortisol secretion, which is often elevated during stress.


from Articles https://ift.tt/3xOoZew
via IFTTT

As detailed in "How COVID Vaccines Can Cause Blood Clots and More," the gene-based COVID-19 injections are a disaster in the making. mRNA-based "vaccines" have been in the works for years, and were never perfected. Now all of a sudden, despite evidence of serious danger, a number of mRNA "vaccines" are in the pipeline.

Among them is a COVID-flu RNA vaccine combo, which is currently being tested on ferrets,1,2,3 and several different mRNA seasonal influenza vaccines,4 which have already entered human trials. As reported by The Verge, July 7, 2021:5

"Moderna gave its mRNA-based seasonal flu vaccine to the first set of volunteers in a clinical trial, the pharmaceutical company announced today. The start of the trial marks the next stage of the company's work on this type of vaccine technology after the overwhelming success of its COVID-19 vaccine, which was built using the same strategy ...

People who get an mRNA vaccine are injected with tiny snippets of genetic material from the target virus. Their cells use that genetic information to build bits of the virus, which the body's immune system learns to fight against …

Moderna is the second group to start testing its mRNA flu shot in human trials — Sanofi and Translate Bio kicked off a trial this summer. Pfizer and BioNTech have been interested in mRNA flu shots for a few years, and they're pushing forward with those plans as well."

Moderna Tests Quadrivalent mRNA Flu 'Vaccine'

Moderna plans to enroll 180 participants aged 18 and older in its Phase 1/2 randomized, stratified, observer-blind, dose-ranging6 study of mRNA-1010, a quadrivalent flu "vaccine" that aims to protect against seasonal influenza A H1N1, H3N2 and influenza B Yamagata and Victoria.

In a press release, Moderna's CEO Stephanie Bancel stated the company hopes to be able to create combination vaccines to protect against several different infections at the same time, such as influenza, COVID-19 and other respiratory infections:7

"Respiratory combination vaccines are an important pillar of our overall mRNA vaccine strategy," Bancel said. "We believe that the advantages of mRNA vaccines include the ability to combine different antigens to protect against multiple viruses and the ability to rapidly respond to the evolution of respiratory viruses, such as influenza, SARS-CoV-2 and RSV.

Our vision is to develop an mRNA combination vaccine so that people can get one shot each fall for high efficacy protection against the most problematic respiratory viruses."

The rapid push to replace conventional flu vaccines with mRNA-based alternatives — before mRNA COVID shots have even been licensed — raises the question, and risk, of whether mRNA flu shots might be getting emergency use authorization (EUA) next.

Worldwide, 3 million to 5 million people come down with influenza, which places "substantial burden on health care systems," according to Moderna,8 so it's not hard to imagine the U.S. Food and Drug Administration giving EUA to any number of shots under the justification that we need to protect the health care system from being overloaded with respiratory infection cases.

Vaccines and Virus Interference

Whether combo mRNA shots against several different types of respiratory viruses will actually work or have an even worse disaster potential than the COVID shots remains to be seen. What we do know is that conventional flu vaccines have the potential to cause viral interference with the mRNA COVID shots, essentially making you more prone to severe COVID-19 if you've received a conventional flu vaccine.

We discussed this in my May 2020 interview with Judy Mikovits, Ph.D. Dr. Michael Murray, a naturopathic physician and author, also pointed this out in his blog post, "Does Flu Shot Increase COVID-19 Risk?"9 The trend was particularly evident in Italy at the beginning of the COVID pandemic, where many elderly succumbed to the infection.

As it turns out, Italy had introduced a new, more potent type of flu vaccine, called VIQCC, in September 2019. VIQCC is produced using cultured animal cells rather than embyonated chicken eggs, which gives a greater boost to the immune system. It also contains four types of influenza viruses.10 "It looks like this 'super' vaccine impacted the immune system in such a way to increase coronavirus infection through virus interference," Murray wrote.

Lessons From the 2009 Swine Flu Pandemic

The kind of virus interference Murray was referring to had been shown to be at play during the 2009 pandemic swine flu. A 2010 review11,12 in PLOS Medicine led by Dr. Danuta Skowronski, a Canadian influenza expert with the Centre for Disease Control in British Columbia, found the seasonal flu vaccine increased people's risk of getting sick with pandemic H1N1 swine flu and resulted in more serious bouts of illness.

People who received the trivalent influenza vaccine during the 2008-2009 flu season were between 1.4 and 2.5 times more likely to get infected with pandemic H1N1 in the spring and summer of 2009 than those who did not get the seasonal flu vaccine.

To double-check the findings, Skowronski and other researchers conducted a follow-up study on ferrets. Their findings were presented at the 2012 Interscience Conference on Antimicrobial Agents and Chemotherapy.

In all, five observational studies conducted across several Canadian provinces found identical results. These findings also confirmed preliminary data from Canada and Hong Kong. As Australian infectious disease expert professor Peter Collignon told ABC News:13

"Some interesting data has become available which suggests that if you get immunized with the seasonal vaccine, you get less broad protection than if you get a natural infection …

We may be perversely setting ourselves up that if something really new and nasty comes along, that people who have been vaccinated may in fact be more susceptible compared to getting this natural infection."

Flu Vaccination Raises Unspecified Coronavirus Infection

Virus interference was also demonstrated in a January 2020 study14,15 which found Department of Defense personnel who were vaccinated against influenza were significantly more likely to contract other respiratory viruses, including unspecified coronavirus infections and human metapneumovirus (hMPV16).

Service members who had received a seasonal flu shot during the 2017-2018 flu season were 36% more likely to contract coronavirus infection and 51% more likely to contract hMPV infection than unvaccinated individuals.17,18 As it turns out, hMPV is one of the respiratory viruses Moderna plans to combat using mRNA combination shots.19

Another is respiratory syncytial virus (RSV), which is similar to coronavirus. RSV is yet another virus shown to be very difficult to prevent with a vaccine. RSV vaccine experiments done in the 1960s ended in disaster, as several of the children studied developed antibody-dependent enhancement (ADE) and died from the resulting cytokine storm when exposed to the wild virus.20

Considering influenza antibodies increase your risk for hMPV and coronavirus infection, and an RSV vaccine has yet to be developed due to the well-known risk of RSV vaccine-enhanced disease, why is Moderna focusing on making an mRNA shot against all four viruses at the same time?

COVID-19 Shots Confer Narrow Immunity

The problem that all of these studies highlight is that influenza vaccination confers very narrow immunity against a specific viral strain, leaving your body open to other viruses. The mRNA shots confer even more specific immunity, as your body is responding to the antigen alone rather than the whole virus.

When it comes to SARS-CoV-2 — which appears to be a genetically manipulated virus designed to attack your cardiovascular system and basic immune function — the spike protein is actually the most dangerous part. This explains why so many are having serious side effects from these COVID shots. The spike protein acts as a toxin in and of itself.

The question is: If you instruct your body to develop a narrow range of antibodies against, say, SARS-CoV-2, a couple of influenza strains, along with hMPV and/or RSV, will that make you more susceptible to other far more serious infections? Or will they start canceling each other out or cause cross-reactions?

Might such a combination exhaust and destroy your immune system entirely? These are just some of the questions that come to mind, based on what we've seen happen with other conventional vaccines and the current mRNA shots for COVID.

Pfizer Requests EUA for Third Booster Dose

Pfizer plans to ask for EUA authorization for a third COVID booster shot in August 2021, Bloomberg reports.21 According to Pfizer's head of research, Mikael Dolsten, initial data suggest a third dose of the current Pfizer shot can raise neutralizing antibody levels by anywhere from fivefold to 10-fold.22 The company is also working on variant-specific formulations.

The booster would be given six to eight months after the second dose. Dolsten points to data from Israel, where Pfizer's mRNA injection was used exclusively, which shows a recent uptick in breakthrough cases. This suggests protection starts to wane around the six-month mark, although Dolsten said it still appears to offer good protection against more severe illness.

For now, the FDA is shying away from authorizing boosters, saying the current shots appear effective enough. In a joint statement published July 8, 2021, the Centers for Disease Control and Prevention and FDA stated:23

"Americans who have been fully vaccinated do not need a booster shot at this time. We are prepared for booster doses if and when the science demonstrates that they are needed."

The way things have been going, though, there's no doubt in my mind they'll greenlight an entire line of boosters for emerging variants. The call for boosters will probably grow in tandem with recognized breakthrough cases, which will be interpreted as waning immunity rather than a sign of outright vaccine failure or ADE.

Freedom Based on the Drugs You Accept

Another reason why I'm certain booster shots will gain EUA authorization is because the treadmill of boosters will support the stated "need" for vaccine passports to keep track of them all. Let's face it, vaccine passports are really pharmaceutical passports.

Eventually, they will dictate what you can and cannot do based on what pharmaceutical products and treatments you accept. Beyond that, they're part of a much larger social credit system, where any infraction will sorely limit your freedom. As noted by former Clinton adviser and author Naomi Wolf in a Fox News interview:24,25

"It is not about the vaccine, it's not about the virus, it's about your data … What people have to understand is that any other functionality can be loaded onto that platform with no problem at all. It can be merged with your Paypal account, with your digital currency.

Microsoft is already talking about merging it with payment plans. Your network can be sucked up. It geolocates you everywhere you go. Your credit history can be included. All of your medical and health history can be included.

This has already happened in Israel, and … we're hearing from activists that it's a two-tiered society and that basically, activists are ostracized and surveilled continually. It is the end of civil society, and they are trying to roll it out around the world.

It is absolutely so much more than a vaccine pass … I cannot stress enough that it has the power to turn off your life, or to turn on your life, to let you engage in society or be marginalized."

Wolf also pointed out the horrific history of IBM,26 whose Digital Health Pass will tie biometric IDs to health data through its smartphone app. This "health pass" will then grant or deny you access to public spaces and events, based on your vaccination status.

This is essentially the modern-day version of the punch card system — the forerunner to digital entry on computers — that IBM developed for the Nazi regime, which allowed them to create a census of Jews and other undesirables, who could then be identified, tracked and sorted into groups slated for incarceration or extermination.

Not only did IBM survive past the end of the war, despite having played an integral role in the genocide, it has now been chosen to create an identical but more technologically advanced copy of the identification and tracking system it created for the Nazi regime. Somehow, that doesn't strike me as entirely accidental. To learn more about IBM's frightening track record, see "IBM Colluded With Hitler, Now Makes Vaccine Passports."

Combating Zoonotic Transmission With Transmissible Vaccines

Disturbingly, in addition to the extremely dangerous mRNA COVID "vaccines" we're now being coerced into taking, we're also facing a future of transmissible vaccines, which would erase free will and informed consent altogether.

The promise of transmissible vaccines is detailed in a January 2021 article in the journal Virus Evolution,27 where they discuss "the development of recombinant viral vaccines that are transmissible, and thus capable of self-dissemination through hard to reach populations of wild animals."

According to mathematical models, transmissible vaccines would significantly reduce the effort required to control pathogens in animal reservoirs, and by lowering the infection rate there, chances of human infection would be diminished. The problem, however, is that vaccination puts the pathogen under evolutionary pressure, which speeds up mutations. Here's how the authors describe it:28

"A key challenge facing these new vaccines … is the inevitability of evolutionary change resulting from their ability to self-replicate and generate extended chains of transmission. Further, carrying immunogenic transgenes is often costly, in terms of metabolic burden, increased competition with the pathogen, or due to unintended interactions with the viral host regulatory network.

As a result, natural selection is expected for favor vaccine strains that down-regulate or delete these transgenes resulting in increased rates of transmission and reduced efficacy against the target pathogen.

In addition, efficacy and evolutionary stability will often be at odds; as when longer, more efficacious antigens experience faster rates of evolutionary decay … However, we find that, at least in some cases, vaccine stability and overall performance can be improved by the inclusion of a second, redundant antigen."

Interestingly enough, the authors include COVID-19 in their list of "zoonoses for which the risk of spillover could possibly be reduced or eliminated through the use of transmissible vaccines." However, as detailed in Dr. Steven Quay's Bayesian analysis,29 SARS-CoV-2 has not been found in any of the 80,000 samples taken from 209 different animal species.

This fact alone proves SARS-CoV-2 is laboratory derived and did not occur through zoonotic spillover. Moreover, none of the first 259 cases in China were traced back to animal contact.30 All were human-to-human transmissions. It's understandable that researchers would allude to their work being beneficial against COVID-19 though, seeing how it has completely taken over the global dialogue.

Are Human Transmissible Vaccines Next?

What bothers me most about the development of transmissible vaccines is that it's only a matter of time before they'll be used in the human population. I predict transmissible vaccines will be the next big thing after mRNA "vaccines."

In a best-case scenario (and it's far from good), transmissible vaccines could be rolled out if COVID-19 shots were to become mandatory worldwide. In a worst-case scenario, they might be introduced even in the absence of a global vaccine mandate. In either case, you can kiss medical freedom goodbye.

Anecdotal evidence of spike protein or exosome transmission between people who have gotten the COVID shot and those who have not also raises the question of whether transmissible vaccines are here already.

While that's still speculative, we can be sure that mRNA flu "vaccines" that turn your body's cells into antigen factories are coming. Scientists have locked in on this transhumanist model of altering your God given genetic instructions rather than preventing illness through healthy lifestyles and treatments using safe medicines.


from Articles https://ift.tt/3zgFLTV
via IFTTT

1 Recent animal research shows the SARS-CoV-2 spike protein can cause myocarditis by:

  • Triggering an exaggerated immune response — a cytokine storm — in the heart cells

    Animal research shows the SARS-CoV-2 spike protein subunit directly damages the heart and causes myocarditis by triggering an exaggerated immune response — a cytokine storm — in the heart cells. Learn more.

  • Permanently attaching to and poking holes in the heart cells
  • Activating the innate immune system
  • Deactivating the ACE2 receptor on the heart cells

2 Powerful investment firms are purchasing a sizeable number of U.S. homes, often over asking price, in order to:

  • Offer them back to Americans at a discounted price
  • Turn them into single-family rentals

    While they're competing with middle-class Americans for the homes, the average American has no chance of winning a home over an investment firm, which may pay 20% to 50% over asking price, in cash, sometimes scooping up entire neighborhoods at once so they can turn them into rentals. Learn more.

  • Ensure that everyone has a place to live
  • Equitably distribute them to low- and middle-class families

3 What's at stake if society truly goes cashless?

  • Loss of your local bank
  • Hidden fees could become the norm
  • Your privacy and your freedom

    But, in the DW documentary "Cash or Card — Will COVID-19 Kill Cash?" producer Kersten Schüssler asks some important questions, like what's at stake if society truly goes cashless? The answer is both your privacy and your freedom. Learn more.

  • You'll have to upgrade your cellphone annually

4 What is the Fourth Industrial Revolution?

  • Reverting from chemical to organic and biodynamic farming
  • A mind-body-spirit centered approach to medicine
  • The transition to individualized medicine
  • The merger of digital, physical and biological systems, and the reliance on technological surveillance rather than the rule of law to maintain public order

    The Fourth Industrial Revolution refers to the merging of digital, physical and biological systems, and the reliance on technological surveillance rather than the rule of law to maintain public order. The Fourth Industrial Revolution will transform not only how we live and interact but who we are as a human species, as man will ultimately be merged with machine. Learn more.

5 Which of the following are totalitarian brainwashing tactics routinely deployed in American institutions of learning?

  • Focus on race and gender divisions and political correctness

    Totalitarian brainwashing tactics routinely deployed in American institutions of higher education include anti-American propaganda, the creation of race and gender divisions, the promotion of collective guilt and stifling political correctness enforced through shaming and cancel culture. Learn more.

  • Forcing students to read classical works of fiction
  • Memorizing the U.S. Constitution
  • Comparing systems of government within a historical context

6 There are several ways to make a virus more lethal. According to Dr. Steven Quay, one way to do that is to:

  • Genetically manipulate the virus with mouse cells in a lab and then release the cells in a human vector
  • Insert a new synthetic amino acid into a pathogen and then do what is called a "serial passage" that passes through a series of animal and human tissues

    If you know what you want to alter, you can insert a new synthetic amino acid into the pathogen. If you don't have a precise idea of the change you want to achieve, but you want the pathogen to adapt from an animal to a human, you can do what is called serial passage, where the virus is passed through a series of animal and human tissues. Learn more.

  • Cross the virus with a known pathogen and allow the pathogen to mutate
  • Allow the virus to grow unhindered with the help of carcinogenic compounds and splice it into the DNA of another dangerous pathogen


from Articles https://ift.tt/2VRDe3X
via IFTTT

In this interview, Dr. Steven Quay — one of the most-cited scientists in the world1 — discusses his Bayesian analysis,2 published January 29, 2021, which concludes beyond a doubt that SARS-CoV-2 is laboratory derived. Quay is an M.D. with a Ph.D. in chemistry. You can learn more about Dr. Quay on his website.

He did his medical residency at Mass General at Harvard Hospital and his postdoctoral work at MIT with a Noble laureate. He holds 87 patents in 22 fields of medicine, including the gadolinium used with MRI imaging.

During his career, Quay published 360 papers, which have been cited over 10,000 times. His COVID origin paper, however, has already been downloaded 170,000 times. Bayesian analysis,3 or Bayesian inference, is a statistical tool used to answer questions about unknown parameters by using probability distributions for observable data.

Quay's highly conservatively-skewed analysis shows there's only a 0.2% likelihood that this virus came from nature, and a 99.8% probability that it came from a lab. His 140-page paper can be downloaded from zenodo.org4 for those who want to dive into the nitty gritty of this statistical analysis. He presented these data to House Representatives during a June 26, 2021, subcommittee on the coronavirus crisis meeting.5

Instead of using the observed statistics of the data he gathered, he radically reduced the probability to 1 in 20. When one combines all the statistical anomalies from the 26 different data points he collected, the real likelihood of the virus coming from nature is less than 1 in all the atoms of the universe — 1080 — which is a very, very large number, making it virtually impossible.

SARS-CoV-2 Has a Protein Sequence Found in Bee Venom Toxin

As early as January 2020, Quay knew SARS-CoV-2 could be problematic. 

"Nobody was paying any attention because there was no need to at that point," he says. "I saw this virus coming out of China. I looked at the sequence of it and I remember telling my wife, 'I know what this thing is going to do in cells,' because for five years at Stanford, I was studying and was the world expert on the toxin melittin, which is a bee venom toxin, the thing that hurts when you get a bee venom …

This melittin, this toxin in bee venom, has the same sequence that SARS-CoV-2 had … I run a public company, so I went to the board a couple weeks later and said, 'Look, I think we can come up with some therapeutics and some ideas around this.' We actually are in clinical trials with some products for therapeutics against SARS-CoV-2.

Then I started hearing some really crazy public health advisories around masks, social distancing and things, so I ended up writing a little book that was a No. 1 best seller for a few weeks called 'Stay Safe: [A Physician's Guide to Survive Coronavirus,]' on Amazon. That took me through the summer. Then I started going back to something. I was very concerned about what I saw as properties of this virus that had never been seen before.

It's now public knowledge that the government identified one of my papers, so I was contacted by the State Department in the fall and basically was an adviser to their programs there, including a three-hour deep dive from all of the different committees or agencies there …

I continue to push this because … if it came from nature, there are certain things we should do differently to not have this happen again. If it came from a laboratory, there's a completely different set of things you need to do. It's not a blame game."

There Are Several Ways to Make a Virus More Dangerous

Quay recently published another paper in which he reveals that the Wuhan Institute of Virology (WIV) is also working on another virus, the Nipah virus, which has a 90% lethality rate. It doesn't take a genius to figure out what might happen if a virus with that lethality got out. Quay explains:

"[The WIV] published an early paper on samples from COVID patients in the hospital … It's the most-read paper from the beginning of the pandemic. I did a deep dive into their raw data. The sequence is 30,000 nucleotides — the raw data's 55 million nucleotides. What you can see in there is a fingerprint of everything they've been doing for the last two years. They're doing a lot of crazy research."

As explained by Quay, the WIV has been around for about 40 years. In 2003, after SARS-Cov-1 emerged, the U.S. and France helped China refurbish the WIV into a more secure BSL 4 biolab, the only one in China. Since then, the WIV has become a primary laboratory for zoonotic viruses. It's also one of the top three laboratories for gain-of-function synthetic biology, which can be accomplished in several ways.

If you know what you want to alter, you can insert a new synthetic amino acid into the pathogen. If you don't have a precise idea of the change you want to achieve, but you want the pathogen to adapt from an animal to a human, you can do what is called serial passage, where the virus is passed through a series of animal and human tissues. 

For example, you could start by infecting 20 humanized mice with a virus, then isolate the virus from the sickest mouse and give it to another 20. Humanized mice are genetically modified mice to have human lung tissue. After four or five passages like that, the virus will have mutated to attack and kill human hosts.

"The third way is to drop big chunks of material in there. For example, the part of the virus of SARS-CoV-2 that interacts with the cell is about 200 amino acids, so times three for nucleic acid, so that's 600. You can just drop a big piece of 600 in and instantly go from an animal to humans, or whatever direction you want.

So, those are the three [primary strategies]: Knowing what to do with single spots, randomly letting nature do it in serial passage, and then dropping big chunks in."

The Bayesian Theorem

As mentioned, Bayesian analysis is a statistical tool using probability distributions. The theorem was developed by Thomas Bayes, a 17th century Presbyterian minister and statistician-mathematician who published many papers during his lifetime. After his death, his estate discovered private notes detailing a process for understanding large complex events in a simple straightforward fashion. The Bayesian equation is A multiplied by B, divided by C. Quay explains:

"It's exactly the same thing we do when we have a favorite baseball team and we watch it during the season. Before the season, we know what they did last year. We know who the new players are, the new coaches, all those things, and we come up with what we call a prior prediction.

We rank the teams according to what we think will happen at the World Series, and that's what's called our prior, our posterior probabilities. Then the season happens and you start winning games, losing games, people get injured, new players, transfers, and you update that every week.

At the start of the World Series, you're probably quite far from where you were at the beginning of the season, because you're now down to two teams but, nonetheless, you still don't know the final analysis. One of the caveats for this 140-page work is, at the end, although I say there's a 1 in 500 chance it came from nature, but that means … 499 times out of 500 it came from a laboratory."

Bayesian Analysis of SARS-CoV-2 Origin

With regard to SARS-CoV-2, "A" would be the prior estimate of the likelihood of it coming from a lab or from nature. "B" is the new evidence, the new probability that it came from a lab, and "C" is the probability that it came from nature. When you multiply A and B and divide it by C, you get a new A prime, a single probability. However, as new data accumulate, the answer changes.

"The first thing I did was assume the prior likelihood it came from nature or a lab, knowing nothing, basically. That has to be your starting point. Three papers informed that. One paper says that eight times a year, there's a natural jump from nature to a human.

Another paper said, once a year, there's a lab leak in Asia, so 8-to-1 [in favor of natural origin]. That's like 85% probability [that it came] from nature. I used three papers, and my starting point was a 98% probability it came from nature, knowing nothing else."

Quay did not include the three papers mainstream media and fact checkers have leaned on to debunk the lab origin theory, and in his paper he explains why they were excluded. In short, they relied on speculation and not science, so the clear bias and lack of scientific facts made them too unreliable.

Next, he entered 26 different pieces of evidence into the equation. The first piece of data was the fact that the virus first emerged in Wuhan, China, which has never happened before. Wuhan has a population of 11 million people. It's a very urban area with little man-nature contact. Wuhan also has one of only three biosafety level (BSL) 4 laboratories in the world that are conducting coronavirus research specifically. Next, he calculated probabilities.

"You know the area of China; you know the population of China. If the virus happened randomly, what is the chance it would happen in Wuhan? If there's a laboratory in Wuhan, what are the chances it would have escaped somewhere else in China and not appeared in Wuhan?

You do the flip. If it came from nature, why did it end up in Wuhan? If it came from Wuhan, what is the probability it could have first appeared somewhere else in China? That hits your probabilities pretty hard out of the box. That was item No. 1. Then you just work through the others."

Zoonotic Transmission

One key piece that makes a big difference in this Bayesian calculation is the question of zoonosis. In order for zoonosis to apply, you must have an animal with a backbone (vertebrae) that is infected with a microbe. Malaria, for example, is not a zoonotic disease, because mosquitoes do not have vertebrae. Malaria is a vector-transmitted disease.

The key to finding the origin of a zoonotic transmission is to locate the animal. If the animal is in the community, then zoonotic transmission occurs through a natural process. If the transmission occurs in a lab, then it's a laboratory-acquired infection, not a zoonotic transmission. Early on, we were told up to 70% of the earliest COVID patients had visited one or more markets in Wuhan, some of which have live animals for sale.

The problem is SARS-CoV-2 was not found in any of the more than 1,000 animal specimens collected from those markets. They also sampled more than 1,000 pieces of frozen food imported from outside of China, all of which came back clean. About 15% of environmental samples, however, did have the virus.

They also collected samples from all the other markets across the Hubei Province, where Wuhan is located. No virus. About 1,000 bats in Hubei were tested, and no virus was found. Over 80,000 animals representing 209 species from every province of China were eventually tested, and no SARS-CoV-2 was found.

For comparison, SARS-1 was found in 85% of animals tested. The original host was identified as the civet cat. MERS, which came from the Middle East, originated in a bat that had jumped to a camel before turning into a human virus, and it was found in 90% of animals. Yet, after the largest surveillance ever conducted in the history of the world, having tested 80,000 animal specimens, not one has been found to carry SARS-CoV-2.

"In my Bayesian analysis … even though I should drop 80,000 into the denominator of my equation, what I did was I degraded it to the standard in clinical trials of biology to a P of .05. I said, 'Despite the fact that zero out of 80,000 had this [virus], I'm going to treat this as if it's a 1 in 20 event,' because that's the only way I could keep doing the analysis. Otherwise, I was done at the get-go," Quay explains.

To be clear, this gives a very unfair advantage to the zoonotic origin theory, but Quay wanted to have a complete analysis of all the parameters. Diversity is a hallmark of nature, yet there's no diversity in nature for this virus. Zoonotic proponents have argued that the virus must be found in high concentration in an intermediate species, yet not one out of 80,000 samples from 209 different animal species is a carrier of the virus.

No Animal Reservoir or Intermediate Host Has Been Found

Another key piece of the analysis is the virus itself. Bats are nature's reservoirs for coronaviruses. The bats are never sickened by them, so the virus is never rooted out. It just lives in the bats for decades, mutating and recombining with other viruses along the way. Bat-to-human contact is very rare, so most of the time, the transfer occurs between the bats, the reservoir host and an intermediate host before it enters the human population.

That's what happened with SARS-1 and MERS. Early cases of SARS-1 and MERS were divided evenly between human to human transmission, and transmissions that occurred between different animals and humans. This means both of these viruses were most likely zoonotic in origin.

As mentioned earlier, Quay cites research showing natural jumps from nature to a human occur eight times a year, and lab escapes occur once a year. That gives us an 8-to-1 chance of zoonotic origin. However, of the first 259 cases in China, not one was traced back to animal contact. All were human-to-human transmissions.

As noted by Quay, "This is the equivalent of going to Las Vegas and flipping a coin and getting heads 259 times. When you ask your statistician to do that, it's a P value with 84 zeros and a number, so again, that's absolutely impossible."

To understand how big this number is, the estimated number of atoms in the universe is 10 to the 80th power. Despite this showing it's more or less impossible for SARS-CoV-2 to have a zoonotic origin, Quay gave this a P value of just 0.5 (or a 1 in 20 chance) — again, just to keep the analysis going.

"It's not in the animals in nature. The virus is a pure virus … It hit the ground with one sequence, and it makes a mistake every two weeks randomly and if it's the kind of mistake it really likes, it keeps it and then that one takes off," he says.

"Again, SARS-1, MERS, every other zoonosis, when it jumps into humans, it's a two-step process. Initially, it jumps into humans, but it doesn't have all the things it needs. It can't make very many baby viruses, et cetera, and so it burns out, and then it tries again, and it tries again. It jumps back to camels, that sort of thing.

Eventually, it gets all the mutations it needs to support human to human transfer. Then you have the foundation for an epidemic, but that's a long process. With SARS-1 it took a year and a half. With MERS, it took two and a half years in camels before it got there. What does that mean though? Every time a human gets an infection … there is a record in their blood. They make antibodies to the virus.

Once you know that a zoonosis is going to jump into humans and leave a record in the hospital specimens and you have a test from the epidemic of the virus itself, you can go back into the hospital and find specimens. Typically, it can range from 1, to 4, to 7, to almost 20% of the specimens.

For example, people working in the market will have antibody evidence that they had the infection, whether they knew it or not.

This is a very powerful tool … Because of the unique capability of this virus to hit human to human transmission from the get-go, [Kristian Andersen, a virologist at the Scripps Research Institute in California who published a paper6 supporting zoonotic origin] predicted that there would be a lot of pre-epidemic seroconversion.

These are fancy words for 'go into a hospital, take samples out of the refrigerator, test them and find a high percentage.' Of course, people took him up on that and tested over 9,900 banked specimens from December [2020] and before in Wuhan. How many do you think they found that were positive?

My statistician says they should have had 100 to 400. They got zero. You run the crank on that, and that's a 1 in a million probability.

The virus has the incredible capability of being the most aggressive human to human virus that's ever been seen in the history of virology, but it does not have the hallmark of how you would build that in nature, which is pre-epidemic human contact. You can't have both of these properties in the same virus if it came from nature.

Now, if you take a mouse that's been humanized in a laboratory to have human lungs and you serial passage there, that is an effective way to do it.

Amazingly, two months after the epidemic broke out, we're February-March 2020 now, Dr. Shi at the Wuhan Institute of Virology and Dr. Baric in America, the No. 1 synthetic biologist in the world of coronavirus research in North Carolina, published a paper saying, 'Hey, if you grow this virus in transgenic mice, it kills the mice and, by the way, they get brain infections, which is really unusual.'

I'm saying, 'Yeah, that's probably the experiment that was done in 2019 that led to the spill.'" 

Again, using extremely conservative data, Quay's analysis shows there's a 99.8% probability that SARS-CoV-2 is a laboratory creation. If you want to read through it all, his paper can be downloaded from zenodo.org.7

Odd SARS-CoV-2 Proteins Suppress Your Immune Function

At the end of the interview, Quay delivers yet another bombshell. SARS-CoV-2 makes three primary kinds of proteins. The first are the structural proteins for a virus — the spike, envelope and nucleoplasm proteins. It also makes proteins that take over the cells' manufacturing process, thereby allowing the virus to replicate inside the cell. In addition to those, it also makes two very odd proteins that are excreted into your blood.

"These strange proteins, they're not the virus, they're not in the cell," Quay explains. "When you get an infection, you get a fever, you get sweaty and you get chills, you feel like crap. That's not the virus. That's your own interferon signaling and it helps you fight the virus and probably in prehistory it told your fellow tribe members to isolate you in your own tent. So, it evolved as a social signal for survival of the tribe."


from Articles https://ift.tt/3ijKlKd
via IFTTT

Dr. Mercola Interviews the Experts

This article is part of a weekly series in which Dr. Mercola interviews various experts on a variety of health issues. To see more expert interviews, click here.

In this interview, return guest Dr. Vladimir Zelenko discusses an incredibly serious concern, one shared with at least two other highly credible experts — Michael Yeadon, Ph.D., a life science researcher and former vice-president and chief scientist of allergy and respiratory research at Pfizer, and professor Luc Montagnier, a world-renowned virologist who won the Nobel prize for his discovery of HIV.

Yeadon, Montagnier and Zelenko all believe the COVID-19 shots could reduce life expectancy by several decades, depending on several factors, including whether you’re required to get booster shots. In fact, there may be reason to suspect that many who get the jabs and subsequent boosters could lose their lives within two to three years, as a result of pathogenic priming.1,2

Many may not realize that when I was a youngster I was a Boy Scout, but you might know their motto is “Be Prepared.” It is an approach that has served me well over the years. I am not stating unequivocally that dire outcome will materialize, as my interview next week with Dr. Peter McCullough goes into. However, it would seem prudent to have a good protocol in your hands in anticipation of a worst-case scenario.

So, on that note, Zelenko and I take a deep dive into what can be done to prevent such a fate. Zelenko categorizes the risks of COVID-19 “vaccines” into three categories: acute, subacute and long-term, so let’s begin by reviewing the primary risks found in each of these categories.

Risk Category No. 1 — Acute Risks

The acute phase of harm begins at the moment of injection and likely lasts for about three months or so. Based on reports filed with the U.S. Vaccine Adverse Event Reporting System (VAERS), it’s clear that many cannot survive past the acute phase.

About 6,000 deaths have been reported so far, and death commonly occurs within 48 hours of injection. Many serious disabling events also occur rather rapidly, typically within a few days or weeks. However, Zelenko has a very dismal perspective on the accuracy of the VAERS database. He explains:

“According to a paper published by the Salk Institute in San Diego, they've discovered that the spike protein that's generated through the vaccination itself has negative health effects. It's toxic … on its own ...

There's plenty of evidence that shows that it spreads from the injection site and goes to the bloodstream, and basically comes into every single cell in the body.3,4

mRNA has a half-life of around one to two weeks, depending on the mRNA, and during that interim, each mRNA molecule makes around 2,000 to 5,000 spike proteins. So, we're talking about trillions and trillions of spike proteins.

Your entire body becomes a spike protein factory. Several orders of magnitude more than if you were to get COVID, because COVID infects the upper and lower airways primarily. Those are the cells that get infected and begin to produce spike proteins. But here we're injecting the vaccine and it actually travels to every single cell in your body and converts every single cell in your body into a factory for spike proteins.”

As the mRNA disseminates through your vascular system, the cells lining your blood vessels begin producing spike protein. This is why we’re seeing such a staggering number of reports of people experiencing blood clots from these injections.

According to Zelenko, 40% of these events occur within the first two days after injection. The risk then diminishes, but vascular events such as heart attacks, strokes, renal infarcts and pulmonary infarcts don’t completely peter out until about three months after the last injection.

But these events of the past three months are not being reported to VAERS. It is, of course, possible that people simply aren’t connecting them to the COVID shot they got several months earlier.

How Many Have Actually Died From the COVID Shots?

As noted by Zelenko, underreporting is part of the problem we’re facing. The real number of side effects is impossible to determine, given the fact that the Food and Drug Administration didn’t insist on a robust post-vaccination data collection system, but it’s most certainly higher than what VAERS is listing.

“If you look at the VAERS [vaccine adverse event reporting system], which in my opinion is a piece of garbage … as of today, let's say says there's 6,000 deaths associated with taking the vaccine. Well, we need to understand what that actually means,” Zelenko says.

“If you look at the 2009 Harvard study on the VAERS system, they said only 1% of events are actually reported. So, OK … whatever the number is, it's not 6,000. Maybe only 10% are being reported. I don't know. But definitely it's being underreported.

And then there's two [additional] big problems. There's evidence coming out that VAERS reports that have been filed are being erased off the server, No. 1. No. 2, I personally know of two dozen cases of deaths associated with the vaccine, and the doctor and/or family members that tried to file a VAERS report, their reports were rejected due to some technicality.

The fact that they all couldn't make a report, that raises my eyebrows. What percentage of the information are we actually seeing? The answer is, I estimate, there are already around 200,000 dead Americans, directly related to the vaccinations.”

To get to that number, Zelenko assumes only 10%5 of adverse effects are reported. Studies have indicated it could be as low as 1%.6,7 That gives us a death toll of about 60,000, to which he adds another 140,000 given the fact that reports are being scrubbed and refused.

“The point is that it should definitely raise eyebrows and have the public start screaming and saying, ‘We want to know the truth. We want to know the accurate numbers. Stop suppressing the truth … I want to be able to make an informed choice whether or not I want to take this injection.’ And that's not being given to the people.

My problem is not with the vaccine. My problem is with the government, governing bodies and certain people that are obstructing the flow of life saving information and suppressing the truth from people, and then using coercion to force people to take this vaccine. That's the nefarious part.

The suppression is so blatant and so overt that doctors with impeccable credentials are being deplatformed for just voicing an opinion. And then you couple that together with proven prehospital treatment approaches and protocols that have been proven to reduce hospitalization and death by 85%, and that information is being suppressed.

So here you have a dual censorship where the positive, hopeful, life-saving information is being suppressed and the dangerous outcomes of the vaccination approach is being suppressed. It's a perfect setup for genocide.”

Risk Category No. 2 — Subacute Risks

The subacute risk phase, which begins around three months’ post-injection, is exceedingly difficult to quantify. At bare minimum, it’s likely to last several months to a couple of years. The primary concern now is antibody-dependent enhancement (ADE), also referred to as pathogenic priming and/or paradoxical immune enhancement (PIE) as it more accurately describes the disease mechanism.

Zelenko believes the mRNA will have degraded by this time, and your cells will hopefully no longer produce spike protein. I believe he may be overly optimistic here, as the synthetic mRNA has been genetically modified to be less perishable, plus it’s encased in a nanolipid to resist breakdown.

I suspect this modified mRNA may remain viable far longer than anyone suspects, thanks to its synthetic nature. What’s more, there’s a mechanism by which the mRNA can be reverse transcribed into your DNA, which would make the spike protein production permanent — and probably intergenerational. I describe this process in “The Many Ways in Which COVID Vaccines May Harm Your Health.”

If Zelenko is correct, then the primary disease agent now switches from the spike protein to the antibodies produced in response to the spike protein. We don’t know how long these antibodies will last, but chances are they’ll stick around for a number of months or years.

While antibody production is the primary purpose of these shots, and the response said to provide you an immune benefit, they can actually be the source of problems.

Animal trials in which conventional coronavirus vaccines were tested have shown coronavirus vaccines routinely cause ADE,8,9,10,11,12 so when the animals are challenged with the real virus they’ve been immunized against, they can get seriously ill and even die. If hospitals start filling up with vaccinated individuals this fall, you’ll know why. They’re suffering the effects of ADE.

“In other words, those antibodies that were produced with the vaccination were pathologic,” Zelenko says. “They were lethal and they led to an exaggerated immune response. That's what it means, antibody-dependent enhancement. It’s an enhancement of your immune response in a way that it will kill you …

The question is, how safe is it long-term, or in the subacute [phase] from three months to three years? That is a big question mark. Based on animal models — and this is what Dr. Mike Yeadon is saying — it could be absolutely genocidal. It's the biggest gamble on the survival of humanity in the history of humanity.”

However, as a counter to this view, Dr. Peter McCullough, who is in complete agreement with the engineering of this event and it being one of the most egregious crimes against humanity, is not convinced that there will be a massive die-off in the fall.

He is well-trained in the science and has essentially completed a fellowship in COVID-19 along with being the senior editor of two prestigious medical journals so his opinion also deserves consideration. We will be posting his interview next Sunday, July 11, 2021.

Why Is Humanity’s Survival Being Risked?

The questions on many people’s mind right now are, “Why are lifesaving early treatment approaches suppressed?” “Why are the toxic side effects and death rates of the vaccines being suppressed?” and “Why are entire continents being coerced into taking a vaccine that is both medically unnecessary and unproven in terms of safety and effectiveness?”

Taken together, none of it makes any sense, which is why people like Yeadon, Montagnier, Zelenko and others are raising concerns about global genocide. Is that what this is all about? Is there an alternative interpretation of what’s happening? When you consider the actual data, mass vaccination simply isn’t necessary, so why the frantic push to get a needle in every arm? Zelenko explains:

“There's something called medical necessity. So, let's analyze if there's any medical necessity for this vaccine, and you have to do that in a systematic way based on demographics.

If you look at the CDC's data, anyone 18 and younger has a 99.998% chance of recovery from COVID-19 with no treatment. [Their risk of dying is] 1 in a million. It’s safer than influenza virus. If you gave me a choice, I would rather my kids have COVID-19 than influenza. So, why would I immunize a demographic that has close to 100% chance of recovery with an experimental vaccine that has already killed more kids than the virus?

If you look at the demographic between 18 and 45, people who are healthy have a 99.95% chance of recovery with no treatment … according to the CDC. Same question, why would I vaccinate a demographic that recovers on its own with no treatment?

Third question, if someone has antibodies — and there's a plethora of evidence [showing] naturally produced antibodies are much more effective in clearing future viruses than vaccine-induced antibodies … Natural immunity is much better, more effective and safer, than vaccine-induced immunity. So, someone who has antibodies already from having COVID before, why would I vaccinate them? …

Fear is an extremely useful tool in manipulating the behavior of people. And that fear has been used to create a psychological motivation to get vaccinated with a vaccine that, in my opinion, has no medical necessity, has tremendous amount of actual and potential risks, and very questionable efficacy.”

Risk Category No. 3 — Long-Term Risks

Beyond the two-to three-year mark are the long-term risks, which are even more difficult to predict. One particularly difficult risk to predict or quantify is infertility. It’ll take decades before we have the data on reproductive effects. Women in their 20s who get the jab might not get serious about trying to get pregnant until they’re in their 30s.

Teens and young children will have to wait decades before fertility can be ascertained. Of course, by then, it’ll be too late. The damage will be done, and hundreds of millions will be in the same boat.

Zelenko cites research published in The New England Journal of Medicine, which concluded COVID vaccination during pregnancy had no increased risk of miscarriage. However, a closer look at the data set revealed that this was only true for women who got vaccinated during their third trimester. Women who get the COVID jab in their first and second trimester have a 24-fold higher risk of miscarriage.

There are also reports of declining sperm counts and testicular swelling in men, and menstrual cycle disruptions in women of all ages. “There is an absolute effect on fertility,” Zelenko says. We just don’t know to what degree yet.

Overall life expectancy is likely to be affected across the board but, again, it’s very difficult to predict just how many years or decades will be lost. Zelenko, like many other doctors, suspect autoimmune diseases and cancer rates will go up as a result of the jabs. As noted by Zelenko:

“Whether you look at the acute spike protein-induced death, the miscarriages, or the myocarditis in young adults, or you look at the subacute pathogenic priming issue, or you look at the potential long-term effects of infertility, auto immune disease and cancer, you have an absolute setup for a genocide. And that's why these world-leading thought leaders, scientists, are cautioning people …

Let's do a thought experiment. If COVID-19 were to infect every single human being on this planet and was not to be treated, what would be the overall global death rate? The answer is less than 1%, and I'm not advocating for that, by the way. That's a lot of people still.

Now, what is going to be the death rate from global vaccination? That is going to be several orders of magnitude greater. And it actually depends how far out you look. Because if someone's meant to live 80 years and they live 60 years, how do you quantify that? …

We're talking about 1.5 to 2 billion people [dying] for no reason, except the agendas of a few psychopaths or sociopaths. Why do I say that? It's because there have been people advocating for population reduction for decades. I just saw a video from [U.K. prime minister] Boris Johnson's father … advocating for the reduction of England's population to 15 million ...

This type of ideology exists. In this generation, it's not really anti-Semitic. What it is, is there's a small group of sociopaths that believe … they've evolved into a superhuman enlightened [state] that entitles them the right to dictate the course of history.

For example, Bill Gates in 2015 said the world population needs to be reduced by a certain percentage because of global warming or whatever. So, my question is a very simple question. He's one of the main supporters and profiteers of global vaccination. Why would I take a vaccine for my health from someone is advocating for the reduction of the world population?

Another scary individual is Klaus Schwab, the founder of the World Economic Forum. He’s very influential. He wrote the book ‘COVID-19 The Great Reset.’ In 2016, in a French interview ... Schwab made an announcement that within 10 years, all of humanity will be tagged with an identifier. If you look at the UN 2030 plan, which was crafted by the World Economic Forum, it says ‘America will no longer be a superpower.’

That's a stated agenda. Then, my favorite is, ‘You'll own nothing and you'll be happy. You won't eat any meat. Fossil fuels will be prohibited. There'll be a billion refugees, which will have to be integrated into your societies.’ So, my question is, what sociopath feels entitled to make a statement like ‘You will own nothing and you will be happy’?

What entitles this type of individual, or group of individuals, to think that way? Well, they believe that they're enlightened far beyond the average human or subhuman.”

War Against God

Zelenko, a devout Jew, believes the root of this global takeover is really a war against God. The implication is that life has sanctity, and if life has sanctity, we have human rights, “earned” by our birth alone. This is the source of natural law. And, if we have human rights, handed down by God, then no one has the right to decide how long any one of us should live, or how many people there should be on the planet.

“That's God's prerogative,” Zelenko says. “However, if you take that out and view people as no different than an animal, a Darwinist perspective or eugenics perspective, and basically survival of the fittest is the yardstick that you measure the dominance hierarchy of humanity, in that case, these people feel that they are on top of the pyramid, and that entitles them to decide if you and me should live …

I call the [COVID] vaccine ‘Zyklon-V.’ That is the gas the Nazis used to kill my relatives. So to express my sentiments, I call it Zyklon-V. It's an absolute weapon of mass destruction. People are being lied to, and they're running into the gas chambers themselves because of the pathogenic fear.”

How to Protect Your Health Post-Jab

If you or someone you know or love got the COVID jab and now have serious regrets, there are definite strategies you can use to protect your health.

It appears if you made it through the first three months OK, then your risk for blood clots is likely radically diminished. To counteract excessive clotting, an anticoagulant may be appropriate. A natural alternative with great promise is n-acetyl cysteine (NAC), as it has both anticoagulant13 and thrombolytic effects,14 meaning it may both prevent clots and break up clots that have already formed. Obviously, do not get any more booster shots.

In the subacute phase, your No. 1 goal will be to avoid ADE. The key to this is to avoid triggering a pathogenic immune reaction, and the only way to do that is to implement some sort of prophylactic protocol, i.e., a COVID, common cold and influenza prevention protocol.

This is especially important for anyone that has received the COVID jab as they are at a high risk of having complications and are under the false impression that they are “protected” when actually they are at increased risk now that they got the jab and need to take extraordinary precautions.

Any symptoms of upper respiratory infection should also be treated immediately, not later. COVID is a multi-phase disease. The first phase is the viral phase, which lasts five to seven days. This is when it’s most easily treated. After Day 7, the disease typically progresses into the inflammatory phase, which requires different treatment.

Zinc supplementation is an important component for prevention and early treatment in the viral stage, as it impairs viral replication. You need to take it with a zinc ionophore, however, such as quercetin, EGCG (green tea extract), hydroxychloroquine or ivermectin.

“The majority of the COVID protocols focus on inhibition of our RNA virus replication. What that means is that for a virus to make copies of itself, it needs to enter the human cell. In the case of RNA viruses, all the COVID, coronaviruses and even the influenza viruses, they use a common pathway called RNA dependent RNA polymerase. That's a very important enzyme.

That enzyme is what makes copies of the viral genetic material, which then enables for new viruses to be formed and spread. So, if you inhibit the viral RNA replication process, you'll eliminate viral spreading, viral growth. The beautiful thing about what we found with zinc is that zinc inhibits this enzyme extremely well, if there's another zinc [molecule] inside the cell.

But zinc cannot really get into the cell on its own. That’s where the concept of zinc ionophores come in. Zinc ionophores opens the door in the cell membrane and allows for zinc to go from outside of the cell, to inside of the cell. And when you increase the concentration of zinc inside the cell, then it can effectively inhibit this enzyme, stopping most if not all, coronaviruses and influenza viruses from replicating.”

If you want to use either hydroxychloroquine or ivermectin and live in a state that restricts their use, look for online telehealth options. The American Frontline Doctors is one resource. They only charge $90 for a consultation and you will be able to get the prescription that you need. Do not use Ivermectin from veterinary sources as it may be contaminated and is not designed for human use.

In addition to zinc and a zinc ionophore, you also need to optimize your vitamin D level. The range you’re looking for is 60 ng/mL to 80 ng/mL year-round. The appropriate dose of oral vitamin D3 is the dose that gets you within that range.

Vitamin C is another important component, especially if you’re taking quercetin, as they have synergistic effects. To effectively act as a zinc ionophore, the quercetin needs vitamin C.

In an effort to make it easier for patients, Zelenko has developed an oral supplement that contains all four: vitamin C, quercetin, vitamin D3 and zinc. It’s called Z-Stack and can be purchased on zstacklife.com. For a downloadable “cheat sheet” of Zelenko’s protocol for COVID-19, visit VladimirZelenkoMD.com.

The take-home message here is that if you’ve gotten the jab, consider yourself high risk for COVID and implement a daily prophylaxis protocol. This means optimizing your vitamin D, and taking vitamin C, zinc and a zinc ionophore on a daily basis, at least throughout cold and flu season.

It would also be useful to do a daily sauna. Ideally one that can heat up to 170 degrees Fahrenheit. The best saunas are far-infrared and have low EMFs. Sadly, I don’t know any that go to 170 degrees and are low EMF.

I use one that goes to 170 and then I turn it off and turn on the SaunaSpace four near IR bulb system in the sauna and go in for 20 minutes. This practice activates heat shock proteins which will help remove the spike proteins and improve other damaged proteins in your body.

If you’re low risk for COVID and have not been vaccinated, make sure you have these items on hand and begin treating at the very first signs of cold or flu symptoms.

Strategies to Lower Risk in Those Who Received COVID Jab

Nebulized hydrogen peroxide 0.1%

Daily or more frequently if needed

NAC (N-acetyl Cysteine)

500 mg once a day

Zinc

15 mg once a day

Vitamin C

500 mg once a day or 250 mg twice a day

Eliminate ALL vegetable (seed) oils

Goal is zero

Vitamin D

Most adults need 8000 IU per day but it is imperative to check blood levels 60-80 ng/ml or 100-150 nmol/l

Daily sauna

20 minutes at 170 degrees will help destroy spike proteins

Time restricted eating

Helps remove spike proteins through autophagy

Seek to eat organic only foods, especially avoid the dirty dozen

This will help limit glyphosate intake

Nebulized Peroxide and Other Health Promoting Measures

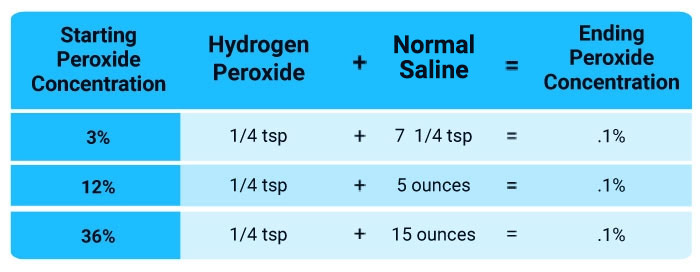
In addition to NAC (to prevent and break up clots), vitamin D, vitamin C, quercetin and zinc, buy yourself a tabletop jet nebulizer, some saline solution and food grade hydrogen peroxide. You’ll want to dilute the peroxide with saline to get a 0.1% solution.

Due to risks to my personal safety we had to remove the nebulized peroxide videos from the site but they are now up on our substack site and you can view all of them here.

hydrogen peroxide dilution chart

Nebulized peroxide is my personal go-to both for prevention and treatment, regardless of the stage the respiratory infection is in. To learn more, download Dr. Thomas Levy’s free e-book, “Rapid Virus Recovery.” As a preventive measure, simply nebulize every other day. Vitamin C is important here too, as it works as a catalyst for the peroxide. A daily dose of 500 milligrams would likely be sufficient for most.

We were forced to remove all the hydrogen peroxide videos that I had previously posted for liability reasons but fortunately they are all now posted on our Substack site. This is important as, in my view, this is the most important step you can take. I would recommend nebulizing a 0.1% solution every day as indicated in the videos, linked below.

There is no danger in doing it every day and likely there is a health benefit. As Dr. Tom Levy describes in one of the videos below, it seems to help improve your bowel movements, which may be a result of eliminating respiratory pathogens that were having negative impact on your microbiome.

hydrogen peroxide videos

>>>>> Click Here <<<<<

Other important health-preserving strategies include the following:

• Make sure you’re metabolically flexible so that your body can seamlessly transition between burning fat and sugar as your primary fuel. This will allow your innate immune system to function optimally. Time-restricted eating is one surefire way to accomplish this.

• Avoid processed seed oils in your diet, such as sunflower oil, corn oil, safflower oil or avocado oils. All contain high levels of linoleic acid, which impairs your mitochondrial function, and in upper respiratory infections, it's the precursor for the Leukotoxin that occurs in these infections.

• Focus on certified-organic foods to minimize your glyphosate exposure, and include plenty of sulfur-rich foods to keep your mitochondria and lysosomes healthy. Both are important for the clearing of cellular debris, including these spike proteins. You can also boost your sulfate by taking Epsom salt baths.

• To combat the toxicity of the spike protein, you’ll want to optimize autophagy, as this may help digest and remove the spike proteins. Time-restricted eating will upregulate autophagy, while sauna therapy, which upregulates heat shock proteins, will help refold misfolded proteins. They also tag damaged proteins and target them for removal.

It is important that your sauna is hot enough (around 170 degrees Fahrenheit) and does not have high magnetic or electric fields.

• If you’re having post-vaccination symptoms, you could consider:

◦ Low-dose interferons such as Paximune, to stimulate your immune system

◦ Peptide T (an HIV entry inhibitor derived from the HIV envelope protein gp120; it blocks binding and infection of viruses that use the CCR5 receptor to infect cells)

◦ Cannabis, to strengthen Type I interferon pathways, which are part of your first line of defense against pathogens

◦ Dimethylglycine or betaine (trimethylglycine) to enhance methylation, thereby suppressing latent viruses

◦ Silymarin or milk thistle to help cleanse your liver


from Articles https://ift.tt/3ripwmf
via IFTTT

MKRdezign

Contact Form

Name

Email *

Message *

Powered by Blogger.
Javascript DisablePlease Enable Javascript To See All Widget