Interest in an occupation matters, but not as much as you might think when it comes to job satisfaction. While it's not a strong predictor of satisfaction, a researcher found that it may help in your performance on the job.
from Top Health News -- ScienceDaily https://ift.tt/35lZENb
With a sharp increase in working from home during the COVID-19 pandemic, more people are noticing age-related skin changes up close on their videoconference calls.
The good news? You don’t need to rush to the dermatologist for your anti-aging needs. The best skincare regimens to combat the cardinal signs of aging, which include uneven skin tone, fine lines, roughness, and dryness, can start from the comfort of your own home. You don’t need a prescription, time to get to a dermatologist, or deep pockets to score quality products.
Here are a few science-backed, dermatologist-favorite ingredients that can help to slow, or even reverse, signs of aging. All of the ingredients listed below can be found over the counter (OTC) and are available in preparations that cost under $30.
The problem? Uneven skin tone. The solution: Topical niacinamide
Niacinamide, or vitamin B3, helps to block extra pigment formation by inhibiting the transfer of melanin (the major pigment in the skin) between skin cells. Applying topical niacinamide (5% concentration) twice a day was shown in a randomized and controlled, split-face trial to reduce freckles and sun spots in as soon as four weeks. The results were maintained throughout the eight-week treatment period. Another clinical study showed improvement of skin redness and sallowness (yellowing of the skin that occurs with age) in people who used topical niacinamide, resulting in a more even complexion. Niacinamide may also improve acne and fine lines.
Topical niacinamide appears to be well tolerated, with no serious side effects.
The problem? Fine lines. The solution: Topical retinoids
Aging can contribute to gradual loss of vitamin A, a retinol, which naturally occurs in the skin. This can be replenished by vitamin A derivatives, known as topical retinoids. Topical retinoids, such as retinol and adapalene, are available over the counter. They have been shown to significantly improve fine wrinkles, likely due to increased skin collagen thickness with prolonged use. Other benefits of retinoids include improvement of dark spots and reduction of atypical skin cells that could lead to skin cancer.
If you have acne or clogged pores, you may want to opt for adapalene, which appears to have more uptake in the follicles where acne starts, and also has anti-inflammatory effects. Both of these factors are important in acne formation. Adapalene may also be less irritating than some other retinoids.
The most common side effects of topical retinoids are dryness, redness, and irritation. This can be mitigated by gradually increasing use (from every third night, to every other night, to nightly), or by avoiding use with other potentially irritating or abrasive products.
Avoid topical retinoids if you are trying to get pregnant, or are currently pregnant or breastfeeding. Also make sure to use an SPF 30+ sunscreen on your face daily, due to increased sun sensitivity with this product.
The problem? Rough or dull skin. The solution: Alpha-hydroxy acids
The very top layers of skin, known as the stratum corneum, may increase in thickness with age, possibly because older cells are less able to renew and turn over. This can lead to skin roughness and can interfere with skin “glow” or luminosity. Alpha-hydroxy acids, such as glycolic acid or lactic acid, are naturally occurring substances that help to break down the bonds between cells in this top layer of skin, which results in smoother skin in as little as 24 hours. Over time, regular use may also improve fine lines, skin yellowing, blotchiness, and dark spots.
Glycolic acid at concentrations of 30% or more is used in the dermatologist’s office as a peel. But there is evidence that OTC preparations at concentrations of around 10% can give you real results and are safe to use at home.
Alpha-hydroxy acids such as lactic acid can also be found in OTC body lotions. They help to smooth the skin from the neck down.
The most common side effect is excess redness, and this can be made worse by using several new, irritating products at once.
The problem? Dry skin. The solution: Hyaluronic acid
An important (but often overlooked) sign of aging skin is dryness. As we age, our skin naturally loses its ability to retain moisture. This is due to decreasing stores of hyaluronic acid, an important component of healthy skin that has the ability to suck in water. Replacing hyaluronic acid through topical serums or moisturizers may help to boost overall skin hydration. Hyaluronic acid can also improve the appearance of wrinkles and skin firmness.
A few parting words
Start slow. If you are new to skincare, you don’t want to start using all of these ingredients at once (this is especially true of using a retinoid and an alpha-hydroxy acid together). Begin in a stepwise fashion, and increase frequency or add additional products only as tolerated. Remember that improvements in skin appearance with any skincare regimen may be subtle and can take time.
Once your skin has become accustomed to these ingredients, consider combination products that combine two or more of the ingredients you’re looking for. Finally, no skincare regimen is complete without good sun protection, so limit sun exposure, wear broad-brimmed hats and sunglasses when outside, and apply daily sunscreen.)
For treatment of deep wrinkles or sagging skin, or for medical skin concerns, seek care from a board-certified dermatologist.
Sleep is crucial for consolidating our memories, and sleep deprivation has long been known to interfere with learning and memory. Now a new study shows that getting only half a night's sleep - as many medical workers and military personnel often do - hijacks the brain's ability to unlearn fear-related memories. That might put people at greater risk of conditions such as anxiety or posttraumatic stress disorder.
from Top Health News -- ScienceDaily https://ift.tt/3knM8Nf
A team of researchers from UTSA's Neurosciences Institute is challenging the historical belief that the organization of the cortical circuit of GABAergic neurons is exclusively local.
from Top Health News -- ScienceDaily https://ift.tt/2GU7HHC
According to a study that examined how informed consent is given to COVID-19 vaccine trial participants, disclosure forms fail to inform volunteers that the vaccine might make them susceptible to more severe disease if they’re exposed to the virus.
The study,1 “Informed Consent Disclosure to Vaccine Trial Subjects of Risk of COVID-19 Vaccine Worsening Clinical Disease,” published in the International Journal of Clinical Practice, October 28, 2020, points out that “COVID-19 vaccines designed to elicit neutralizing antibodies may sensitize vaccine recipients to more severe disease than if they were not vaccinated.”
“Vaccines for SARS, MERS and RSV have never been approved, and the data generated in the development and testing of these vaccines suggest a serious mechanistic concern: that vaccines designed empirically using the traditional approach (consisting of the unmodified or minimally modified coronavirus viral spike to elicit neutralizing antibodies), be they composed of protein, viral vector, DNA or RNA and irrespective of delivery method, may worsen COVID-19 disease via antibody-dependent enhancement (ADE),” the paper states.
“This risk is sufficiently obscured in clinical trial protocols and consent forms for ongoing COVID-19 vaccine trials that adequate patient comprehension of this risk is unlikely to occur, obviating truly informed consent by subjects in these trials.
The specific and significant COVID-19 risk of ADE should have been and should be prominently and independently disclosed to research subjects currently in vaccine trials, as well as those being recruited for the trials and future patients after vaccine approval, in order to meet the medical ethics standard of patient comprehension for informed consent.”
What Is Antibody-Dependent Enhancement?
As noted by the authors of that International Journal of Clinical Practice paper, previous coronavirus vaccine efforts — for severe acute respiratory syndrome coronavirus (SARS-CoV), Middle East respiratory syndrome coronavirus (MERS-CoV) and respiratory syncytial virus (RSV) — have revealed a serious concern: The vaccines have a tendency to trigger antibody-dependent enhancement.
What exactly does that mean? In a nutshell, it means that rather than enhance your immunity against the infection, the vaccine actually enhances the virus’ ability to enter and infect your cells, resulting in more severe disease than had you not been vaccinated.2
This is the exact opposite of what a vaccine is supposed to do, and a significant problem that has been pointed out from the very beginning of this push for a COVID-19 vaccine. The 2003 review paper “Antibody-Dependent Enhancement of Virus Infection and Disease” explains it this way:3
“In general, virus-specific antibodies are considered antiviral and play an important role in the control of virus infections in a number of ways. However, in some instances, the presence of specific antibodies can be beneficial to the virus. This activity is known as antibody-dependent enhancement (ADE) of virus infection.
The ADE of virus infection is a phenomenon in which virus-specific antibodies enhance the entry of virus, and in some cases the replication of virus, into monocytes/macrophages and granulocytic cells through interaction with Fc and/or complement receptors.
This phenomenon has been reported in vitro and in vivo for viruses representing numerous families and genera of public health and veterinary importance. These viruses share some common features such as preferential replication in macrophages, ability to establish persistence, and antigenic diversity. For some viruses, ADE of infection has become a great concern to disease control by vaccination.”
Previous Coronavirus Vaccine Efforts Have All Failed
In my May 2020 interview above with Robert Kennedy Jr., he summarized the history of coronavirus vaccine development, which began in 2002, following three consecutive SARS outbreaks. By 2012, Chinese, American and European scientists were working on SARS vaccine development, and had about 30 promising candidates.
Of those, the four best vaccine candidates were then given to ferrets, which are the closest analogue to human lung infections. In the video below, which is a select outtake from my full interview, Kennedy explains what happened next. While the ferrets displayed robust antibody response, which is the metric used for vaccine licensing, once they were challenged with the wild virus, they all became severely ill and died.
The same thing happened when they tried to develop an RSV vaccine in the 1960s. RSV is an upper respiratory illness that is very similar to that caused by coronaviruses. At that time, they had decided to skip animal trials and go directly to human trials.
“They tested it on I think about 35 children, and the same thing happened,” Kennedy said. “The children developed a champion antibody response — robust, durable. It looked perfect [but when] the children were exposed to the wild virus, they all became sick. Two of them died. They abandoned the vaccine. It was a big embarrassment to FDA and NIH.”
Neutralizing Versus Binding Antibodies
Coronaviruses produce not just one but two different types of antibodies:
Neutralizing antibodies,4 also referred to as immoglobulin G (IgG) antibodies, that fight the infection
Binding antibodies5 (also known as nonneutralizing antibodies) that cannot prevent viral infection
Instead of preventing viral infection, binding antibodies trigger an abnormal immune response known as “paradoxical immune enhancement.” Another way to look at this is your immune system is actually backfiring and not functioning to protect you but actually making you worse.
Many of the COVID-19 vaccines currently in the running are using mRNA to instruct your cells to make the SARS-CoV-2 spike protein (S protein). The spike protein, which is what attaches to the ACE2 receptor of the cell, is the first stage of the two-stage process viruses use to gain entry into cells.
The idea is that by creating the SARS-CoV-2 spike protein, your immune system will commence production of antibodies, without making you sick in the process. The key question is, which of the two types of antibodies are being produced through this process?
Without Neutralizing Antibodies, Expect More Severe Illness
In an April 2020 Twitter thread,6 The Immunologist noted: “While developing vaccines … and considering immunity passports, we must first understand the complex role of antibodies in SARS, MERS and COVID-19.” He goes on to list several coronavirus vaccine studies that have raised concerns about ADE.
The first is a 2017 study7 in PLOS Pathogens, ”Enhanced Inflammation in New Zealand White Rabbits When MERS-CoV Reinfection Occurs in the Absence of Neutralizing Antibody,” which investigated whether getting infected with MERS would protect the subject against reinfection, as is typically the case with many viral illnesses. (Meaning, once you recover from a viral infection, say measles, you’re immune and won’t contract the illness again.)
To determine how MERS affects the immune system, the researchers infected white rabbits with the virus. The rabbits got sick and developed antibodies, but those antibodies were not the neutralizing kind, meaning the kind of antibodies that block infection. As a result, they were not protected from reinfection, and when exposed to MERS for a second time, they became ill again, and more severely so.
“In fact, reinfection resulted in enhanced pulmonary inflammation, without an associated increase in viral RNA titers,” the authors noted. Interestingly, neutralizing antibodies were elicited during this second infection, preventing the animals from being infected a third time. According to the authors:
“Our data from the rabbit model suggests that people exposed to MERS-CoV who fail to develop a neutralizing antibody response, or persons whose neutralizing antibody titers have waned, may be at risk for severe lung disease on re-exposure to MERS-CoV.”
In other words, if the vaccine does not result in a robust response in neutralizing antibodies, you might be at risk for more severe lung disease if you’re infected with the virus.
And here’s an important point: COVID-19 vaccines are NOT designed to prevent infection. As detailed in “How COVID-19 Vaccine Trials Are Rigged,” a “successful” vaccine merely needs to reduce the severity of the symptoms. They’re not even looking at reducing infection, hospitalization or death rates.
ADE in Dengue Infections
The Dengue virus is also known to cause ADE. As explained in a Swiss Medical Weekly paper published in April 2020:8
“The pathogenesis of COVID-19 is currently believed to proceed via both directly cytotoxic and immune-mediated mechanisms. An additional mechanism facilitating viral cell entry and subsequent damage may involve the so-called antibody-dependent enhancement (ADE).
ADE is a very well-known cascade of events whereby viruses may infect susceptible cells via interaction between virions complexed with antibodies or complement components and, respectively, Fc or complement receptors, leading to the amplification of their replication.
This phenomenon is of enormous relevance not only for the understanding of viral pathogenesis, but also for developing antiviral strategies, notably vaccines …
There are four serotypes of Dengue virus, all eliciting protective immunity. However, although homotypic protection is long-lasting, cross-neutralizing antibodies against different serotypes are short-lived and may last only up to 2 years.
In Dengue fever, reinfection with a different serotype runs a more severe course when the protective antibody titer wanes. Here, non-neutralizing antibodies take over neutralizing ones, bind to Dengue virions, and these complexes mediate the infection of phagocytic cells via interaction with the Fc receptor, in a typical ADE.
In other words, heterotypic antibodies at subneutralizing titres account for ADE in persons infected with a serotype of Dengue virus that is different from the first infection.
Cross-reactive neutralizing antibodies are associated with decreased odds of symptomatic secondary infection, and the higher the titer of such antibodies following the primary infection, the longer the delay to symptomatic secondary infection …”
The paper goes on to detail results from follow-up investigations into the Dengue vaccine, which revealed the hospitalization rate for Dengue among vaccinated children under the age of 9 was greater than the rate among controls. The explanation for this appears to be that the vaccine mimicked a primary infection, and as that immunity waned, the children became susceptible to ADE when they encountered the virus a second time. The author explains:
“A post hoc analysis of efficacy trials, using an anti-nonstructural protein 1 immunoglobulin G (IgG) enzyme-linked immunosorbent assay (ELISA) to distinguish antibodies elicited by wild-type infection from those following vaccination, showed that the vaccine was able to protect against severe Dengue [in] those who had been exposed to the natural infection before vaccination, and that the risk of severe clinical outcome was increased among seronegative persons.
Based on this, a Strategic Advisor Group of Experts convened by World Health Organization (WHO) concluded that only Dengue seropositive persons should be vaccinated whenever Dengue control programs are planned that include vaccination.”
ADE in Coronavirus Infections
This could end up being important for the COVID-19 vaccine. Hypothetically speaking, if SARS-CoV-2 works like Dengue, which is also caused by an RNA virus, then anyone who has not tested positive for SARS-CoV-2 might actually be at increased risk for severe COVID-19 after vaccination, and only those who have already recovered from a bout of COVID-19 would be protected against severe illness by the vaccine.
To be clear, we do not know whether that is the case or not, but these are important areas of inquiry and the current vaccine trials will simply not be able to answer this important question.
The Swiss Medical Weekly paper9 also reviews the evidence of ADE in coronavirus infections, citing research showing inoculating cats against the feline infectious peritonitis virus (FIPV) — a feline coronavirus — increases the severity of the disease when challenged with the same FIPV serotype as that in the vaccine.
The paper also cites research showing “Antibodies elicited by a SARS-CoV vaccine enhanced infection of B cell lines in spite of protective responses in the hamster model.” Another paper,10 “Antibody-Dependent SARS Coronavirus Infection Is Mediated by Antibodies Against Spike Proteins,” published in 2014, found that:
“… higher concentrations of anti-sera against SARS-CoV neutralized SARS-CoV infection, while highly diluted anti-sera significantly increased SARS-CoV infection and induced higher levels of apoptosis.
Results from infectivity assays indicate that SARS-CoV ADE is primarily mediated by diluted antibodies against envelope spike proteins rather than nucleocapsid proteins. We also generated monoclonal antibodies against SARS-CoV spike proteins and observed that most of them promoted SARS-CoV infection.
Combined, our results suggest that antibodies against SARS-CoV spike proteins may trigger ADE effects. The data raise new questions regarding a potential SARS-CoV vaccine …”
A study11 that ties into this was published in the journal JCI Insight in 2019. Here, macaques vaccinated with a modified vaccinia Ankara (MVA) virus encoding full-length SARS-CoV spike protein ended up with more severe lung pathology when the animals were exposed to the SARS virus. And, when they transferred anti-spike IgG antibodies into unvaccinated macaques, they developed acute diffuse alveolar damage, likely by “skewing the inflammation-resolving response.”
SARS Vaccine Worsens Infection After Challenge With SARS-CoV
An interesting 2012 paper12 with the telling title, “Immunization with SARS Coronavirus Vaccines Leads to Pulmonary Immunopathology on Challenge with the SARS Virus,” demonstrates what many researchers now fear, namely that COVID-19 vaccines may end up making people more prone to severe SARS-CoV-2 infection.
The paper reviews experiments showing immunization with a variety of SARS vaccines resulted in pulmonary immunophathology once challenged with the SARS virus. As noted by the authors:13
“Inactivated whole virus vaccines whether inactivated with formalin or beta propiolactone and whether given with our without alum adjuvant exhibited a Th2-type immunopathologic in lungs after challenge.
As indicated, two reports attributed the immunopathology to presence of the N protein in the vaccine; however, we found the same immunopathologic reaction in animals given S protein vaccine only, although it appeared to be of lesser intensity.
Thus, a Th2-type immunopathologic reaction on challenge of vaccinated animals has occurred in three of four animal models (not in hamsters) including two different inbred mouse strains with four different types of SARS-CoV vaccines with and without alum adjuvant. An inactivated vaccine preparation that does not induce this result in mice, ferrets and nonhuman primates has not been reported.
This combined experience provides concern for trials with SARS-CoV vaccines in humans. Clinical trials with SARS coronavirus vaccines have been conducted and reported to induce antibody responses and to be ‘safe.’ However, the evidence for safety is for a short period of observation.
The concern arising from the present report is for an immunopathologic reaction occurring among vaccinated individuals on exposure to infectious SARS-CoV, the basis for developing a vaccine for SARS. Additional safety concerns relate to effectiveness and safety against antigenic variants of SARS-CoV and for safety of vaccinated persons exposed to other coronaviruses, particularly those of the type 2 group.”
The Elderly Are Most Vulnerable to ADE
On top of all of these concerns, there’s evidence showing the elderly — who are most vulnerable to severe COVID-19 — are also the most vulnerable to ADE. Preliminary research findings14 posted on the preprint server medRxiv at the end of March 2020 reported that middle-aged and elderly COVID-19 patients have far higher levels of anti-spike antibodies — which, again, increase infectivity — than younger patients.
Immune Enhancement Is a Serious Concern
Another paper worth mentioning is the May 2020 mini review15 “Impact of Immune Enhancement on COVID-19 Polyclonal Hyperimmune Globulin Therapy and Vaccine Development.” As in many other papers, the authors point out that:16
“While development of both hyperimmune globulin therapy and vaccine against SARS-CoV-2 are promising, they both pose a common theoretical safety concern. Experimental studies have suggested the possibility of immune-enhanced disease of SARS-CoV and MERS-CoV infections, which may thus similarly occur with SARS-CoV-2 infection …
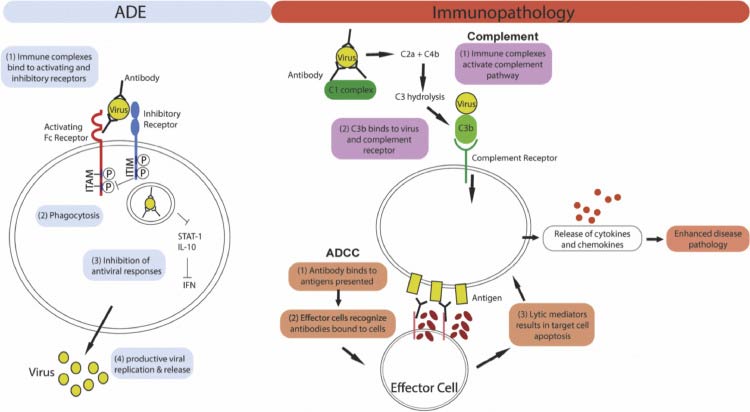
Immune enhancement of disease can theoretically occur in two ways. Firstly, non-neutralizing or sub-neutralizing levels of antibodies can enhance SARS-CoV-2 infection into target cells.
Secondly, antibodies could enhance inflammation and hence severity of pulmonary disease. An overview of these antibody dependent infection and immunopathology enhancement effects are summarized in Fig. 1 …
Currently, there are multiple SARS-CoV and MERS-CoV vaccine candidates in pre-clinical or early phase clinical trials. Animal studies on these CoVs have shown that the spike (S) protein-based vaccines (specifically the receptor binding domain, RBD) are highly immunogenic and protective against wild-type CoV challenge.
Vaccines that target other parts of the virus, such as the nucleocapsid, without the S protein, have shown no protection against CoV infection and increased lung pathology. However, immunization with some S protein based CoV vaccines have also displayed signs of enhanced lung pathology following challenge.
Hence, besides the choice of antigen target, vaccine efficacy and risk of immunopathology may be dependent on other ancillary factors, including adjuvant formulation, age at vaccination … and route of immunization.”
Figure 1: Mechanism of ADE and antibody mediated immunopathology. Left panel: For ADE, immune complex internalization is mediated by the engagement of activating Fc receptors on the cell surface. Co-ligation of inhibitory receptors then results in the inhibition of antiviral responses which leads to increased viral replication. Right panel: Antibodies can cause immunopathology by activating the complement pathway or antibody-dependent cellular cytotoxicity (ADCC). For both pathways, excessive immune activation results in the release of cytokines and chemokines, leading to enhanced disease pathology.
Do a Risk-Benefit Analysis Before Making Up Your Mind
In all likelihood, regardless of how effective (or ineffective) the COVID-19 vaccines end up being, they’ll be released to the public in relatively short order. Most predict one or more vaccines will be ready sometime in 2021.
Ironically, the data17,18,19 we now have no longer support a mass vaccination mandate, considering the lethality of COVID-19 is lower than the flu for those under the age of 60.20 If you’re under the age of 40, your risk of dying from COVID-19 is just 0.01%, meaning you have a 99.99% chance of surviving the infection. And you could improve that to 99.999% if you’re metabolically flexible and vitamin D replete.
So, really, what are we protecting against with a COVID-19 vaccine? As mentioned, the vaccines aren’t even designed to prevent infection, only reduce the severity of symptoms. Meanwhile, they could potentially make you sicker once you’re exposed to the virus. That seems like a lot of risk for a truly questionable benefit.
To circle back to where we started, participants in current COVID-19 vaccine trials are not being told of this risk — that by getting the vaccine they may end up with more severe COVID-19 once they’re infected with the virus.
Lethal Th2 Immunopathology Is Another Potential Risk
In closing, consider what this PNAS news feature states about the risk of vaccine-induced immune enhancement and dysfunction, particularly for the elderly, the very people who would need the protection a vaccine might offer the most:21
“Since the 1960s, tests of vaccine candidates for diseases such as dengue, respiratory syncytial virus (RSV), and severe acute respiratory syndrome (SARS) have shown a paradoxical phenomenon:
Some animals or people who received the vaccine and were later exposed to the virus developed more severe disease than those who had not been vaccinated. The vaccine-primed immune system, in certain cases, seemed to launch a shoddy response to the natural infection …
This immune backfiring, or so-called immune enhancement, may manifest in different ways such as antibody-dependent enhancement (ADE), a process in which a virus leverages antibodies to aid infection; or cell-based enhancement, a category that includes allergic inflammation caused by Th2 immunopathology. In some cases, the enhancement processes might overlap …
Some researchers argue that although ADE has received the most attention to date, it is less likely than the other immune enhancement pathways to cause a dysregulated response to COVID-19, given what is known about the epidemiology of the virus and its behavior in the human body.
‘There is the potential for ADE, but the bigger problem is probably Th2 immunopathology,’ says Ralph Baric, an epidemiologist and expert in coronaviruses … at the University of North Carolina at Chapel Hill.
In previous studies of SARS, aged mice were found to have particularly high risks of life-threatening Th2 immunopathology ... in which a faulty T cell response triggers allergic inflammation, and poorly functional antibodies that form immune complexes, activating the complement system and potentially damaging the airways.”
“It seems gene editing is going to eliminate all disease,” said HBO’s John Oliver, “Or kill every last one of us.”1 He’s referring to gene-editing tools such as CRISPR, or Clustered Regularly Interspaced Short Palindromic Repeat, and TALEN (Transcription Activator-Like Effector Nuclease), which are being used for everything from disease treatment to agriculture.
Unbeknownst to many, CRISPR technology has already been used to tinker with crops, including both plants and animal farming. In addition to altering the taste of foods, CRISPR is being used to extend shelf life and create foods that resist certain bacteria and viruses.2
Even chicken — a staple food in diets around the world — has been eyed for gene editing due to avian leucosis virus, and a “CRISPR” chicken may be coming to your dinner plate soon.
Avian Leukosis Virus Widespread in CAFO Poultry
Avian leukosis virus (ALV) has been plaguing the CAFO (concentrated animal feeding operation) poultry industry since it was first identified in 1991.3 The disease causes tumors to develop in the birds, along with symptoms such as weakness, loss of appetite, diarrhea and depression.4
The last major ALV outbreak occurred in 2018 in China, leading to high mortality rates among infected chickens.5 However, the virus is present in CAFO chickens worldwide, leading to an estimated millions of pounds of losses annually.6
The U.S. Department of Agriculture (USDA) once required that chickens that show signs of ALV or “lesions” (tumors) must be removed from processing so they do not enter the food chain.7
However, the National Chicken Council petitioned the USDA’s Food Safety and Inspection Service in March 2019 asking to “treat lesions that could be suspected as being caused by avian leukosis as a trimmable condition and not a condition that requires whole bird condemnation.”8
July 16, 2020, FSIS accepted the petition, stating, “We have determined that current scientific evidence supports treating avian leukosis as a trimmable condition and that the actions requested in your petition would reduce regulatory burdens on the industry.”9
Despite the significant regulatory change — which means chickens riddled with tumors may still end up in the food supply as long as they’re “trimmed” — researchers have been looking toward gene editing as another way to eradicate ALV from CAFO poultry flocks.
Scientists Use CRISPR to Tackle Avian Leukosis
In 2018, researchers with the Czech Academy of Sciences determined that, because ALVs use specific receptor proteins to gain entry into cells, such receptors would make good targets for “biotechnological manipulation” in order to create poultry resistant to the virus, which they attempted using CRISPR-Cas 9.10
CRISPR gene-editing technology brought science fiction to life with its ability to cut and paste DNA fragments, potentially eliminating serious inherited diseases. CRISPR-Cas9, in particular, has gotten scientists excited because,11 by modifying an enzyme called Cas9, the gene-editing capabilities are significantly improved.
In their 2018 study, published in the journal Viruses, the scientists noted that “CRISPR/Cas9-mediated knock-out or the fine editing of ALV receptor genes might be the first step in the development of virus-resistant chickens.”12 In a separate study published in PNAS in January 2020, the researchers demonstrated that CRISPR-Cas9 was effective in rendering chickens resistant to the J subgroup of ALV. They noted:13
“We introduced a single amino acid deletion into the gene encoding the receptor that is required for avian leukosis virus subgroup J to infect chicken cells. Here, we demonstrate that this mutation confers the resistance of chickens to avian leukosis virus subgroup J, an important pathogen in poultry. In addition, we present highly efficient genome-editing technology in chicken.”
They added that no visible side effects were apparent after the process, which involved deleting tryptophan residue number 38 of chNHE1 (W38), a critical amino acid for virus entry. The word “visible” is key, however, as many unexpected changes may still occur that aren’t immediately recognizable, and it’s possible for those changes to be transferred to other organisms or generations.
In an interview with Yale Insights, Dr. Greg Licholai, a biotech entrepreneur and a lecturer at Yale, explained that this could even lead to problems that are worse than the “cure,” like antibiotic resistance or incurable diseases:14
“That’s probably the biggest fear of CRISPR. Humans manipulating the genetic code, and those manipulations get passed on generation to generation to generation.
We think we know what we’re doing, we think we’re measuring exactly what changes we’re doing to the genes, but there’s always the possibility that either we miss something or our technology can’t pick up on other changes that have been made that haven’t been directed by us.
And the fear then is that those changes lead to antibiotic resistance or other mutations that go out into the population and would be very difficult to control. Basically creating incurable diseases or other potential mutations that we wouldn’t really have control over.”
Gene-Edited Chickens Also Exist That Resist Flu
Influenza spreads rapidly among CAFO birds and has the potential to be transmitted to humans. The simplest way to stop the widespread transmission of bird flu would be to change the way chickens are raised, putting them outdoors on pasture as opposed to crowded in disease-ridden CAFOs.
Scientists, however, turned to biotechnology instead, using CRISPR to target part of the ANP32 gene, which codes for a protein that flu viruses depend on,15 in order to create flu-resistant chickens.16
Flu- and ALV-resistant chickens are just two examples of gene-editing technology at work. Researchers have also snipped out a section of pig DNA intended to prevent porcine reproductive and respiratory syndrome (PRRS) — a common and often fatal ailment among CAFO pigs.17 Such edits are permanent and passed down to other generations.
In another project, this one funded by the USDA, researchers have added the SRY gene to cattle, which results in female cows that turn into males, complete with larger muscles, a penis and testicles, but no ability to make sperm.18 Male (or male-like) cattle are more valuable to the beef industry because they get bigger, faster, allowing companies to make greater profits in less time.
Other biotech companies have taken to targeting genes intended to ease animal suffering, which they believe may soften regulators and consumers who are wary of the technology.19 One company snipped out the genes responsible for growing horns in dairy cows, for instance, which means they wouldn’t be subjected to the inhumane ways the horns are currently removed (with no pain relief).
As for gene-edited animals, the FDA proposed to classify animals with edited or engineered DNA as drugs,20 prompting backlash from the biotech industry,21 which doesn’t even want such foods labeled. This isn’t the case for gene-edited plants, however, which have largely escaped regulation.
Gene-Edited Mushrooms and Lax Regulations
A number of gene-edited plant foods have also been developed or proposed, including non-browning mushrooms, which were created by Yinong Yang, a plant pathologist at Pennsylvania State University, in 2016 using CRISPR-Cas9. Although the “frankenfungi,” as it’s been called, has never before existed in nature, it would require no USDA approval because it does not contain foreign DNA.
"Our genome-edited mushroom has small deletions in a specific gene but contains no foreign DNA integration in its genome," Yang said in Penn State’s Ag Science Magazine. "Therefore, we believed that there was no scientifically valid basis to conclude that the CRISPR-edited mushroom is a regulated article based on the definition described in the regulations."22
Weeks after the USDA notified Yang that the gene-edited non-browning mushrooms would not require approval, it also ruled that DuPont Pioneer’s CRISPR-Cas9-edited corn would also be able to bypass regulatory approval.23
The rule, known as the "Sustainable, Ecological, Consistent, Uniform, Responsible, Efficient" (SECURE) rule,24 was finalized in May 2020 and maintained the status that crops edited using CRISPR-Cas9 and other similar technologies would be non-regulated.25
Are You Already Eating Gene-Edited Soybean Oil?
A gene-edited soybean oil created by biotech company Calyxt was picked up by its first user — a Midwest company with both restaurant and foodservice locations, which is using it for frying as well as in dressings and sauces — in 2019.26 Calyxt’s soybean oil, Calyno,27 contains two inactivated genes, resulting in an oil with no trans fats, increased heart-healthy oleic acid and a longer shelf life.
As of February 2019, more than 100 farmers in the Midwest were reportedly growing Calyxt’s high-oleic soybeans on more than 34,000 acres.28 In an update released February 7, 2020, Calyxt stated it had contracted 100,000 soybean acres in the U.S. for 2020, which represented 178% growth from the year prior.29
It also received its first purchase order from a customer targeting four of its primary markets (foodservice, food ingredients, animal nutrition and industrial,) and is now offering 1-gallon jugs of its Calyno cooking oil directly to consumers.30
Calyxt has also developed a high-fiber wheat, which has been declared a non-regulated article and may launch as early as 2020 or 2021.31 In short, gene-edited foods are already on the market and expanding with fervor, while the health and environmental risks remain completely unknown.
Unexpected Consequences, Risks Uncovered
Gene-editing, for all of its intended precision, isn’t an exact science. In animals, gene editing has led to unexpected side effects, including enlarged tongues and extra vertebrate.32,33
Further, when researchers at the U.K.’s Wellcome Sanger Institute systematically studied mutations from CRISPR-Cas9 in mouse and human cells, large genetic rearrangements were observed, including DNA deletions and insertions, near the target site. The DNA deletions could end up activating genes that should stay “off,” such as cancer-causing genes, as well as silencing those that should be “on.”34
Without a label requirement, there’s no way for consumers to know whether they’re eating gene edited soybean oil — or one of the many future gene edited products likely to hit the market, like “CRISPR chicken.” For now, however, gene-edited foods cannot be labeled organic, which is one more reason why seeking out organic and, even better, biodynamic foods, is so important.